Background:
Non-AIDS Defining Malignancies (NADM) have become a prominent cause of death in people with HIV (PWH). Evidence shows that starting antiretroviral treatment (ART) at a higher CD4 count is associated with reduced NADM risk. We aimed to investigate whether starting ART early after acquiring HIV reduces NADM risk even further.
Methods:
We included PWH 18 years or older from the Dutch National ATHENA cohort without a known NADM diagnosis starting ART between 1/1/2000–31/12/2022. NADM and infection-related NADM were analyzed separately. Individuals who started ART ≤365 days of a last known negative HIV test or with a documented primary infection (Fiebig stages 1-5) were categorized as ‘Early-ART’, and all others as ‘Late-ART’ starters. Hazard Ratios (HR) for NADM were estimated by unadjusted and adjusted Cox regression. Models were adjusted for traditional (age, sex at birth, calendar time, HIV transmission category, smoking (time-updated), and region of origin) and HIV related (time-updated CD4 count lagged by 3 months, CD4/8 ratio and time spent with HIV RNA >1000 copies/ml) factors.
Results:
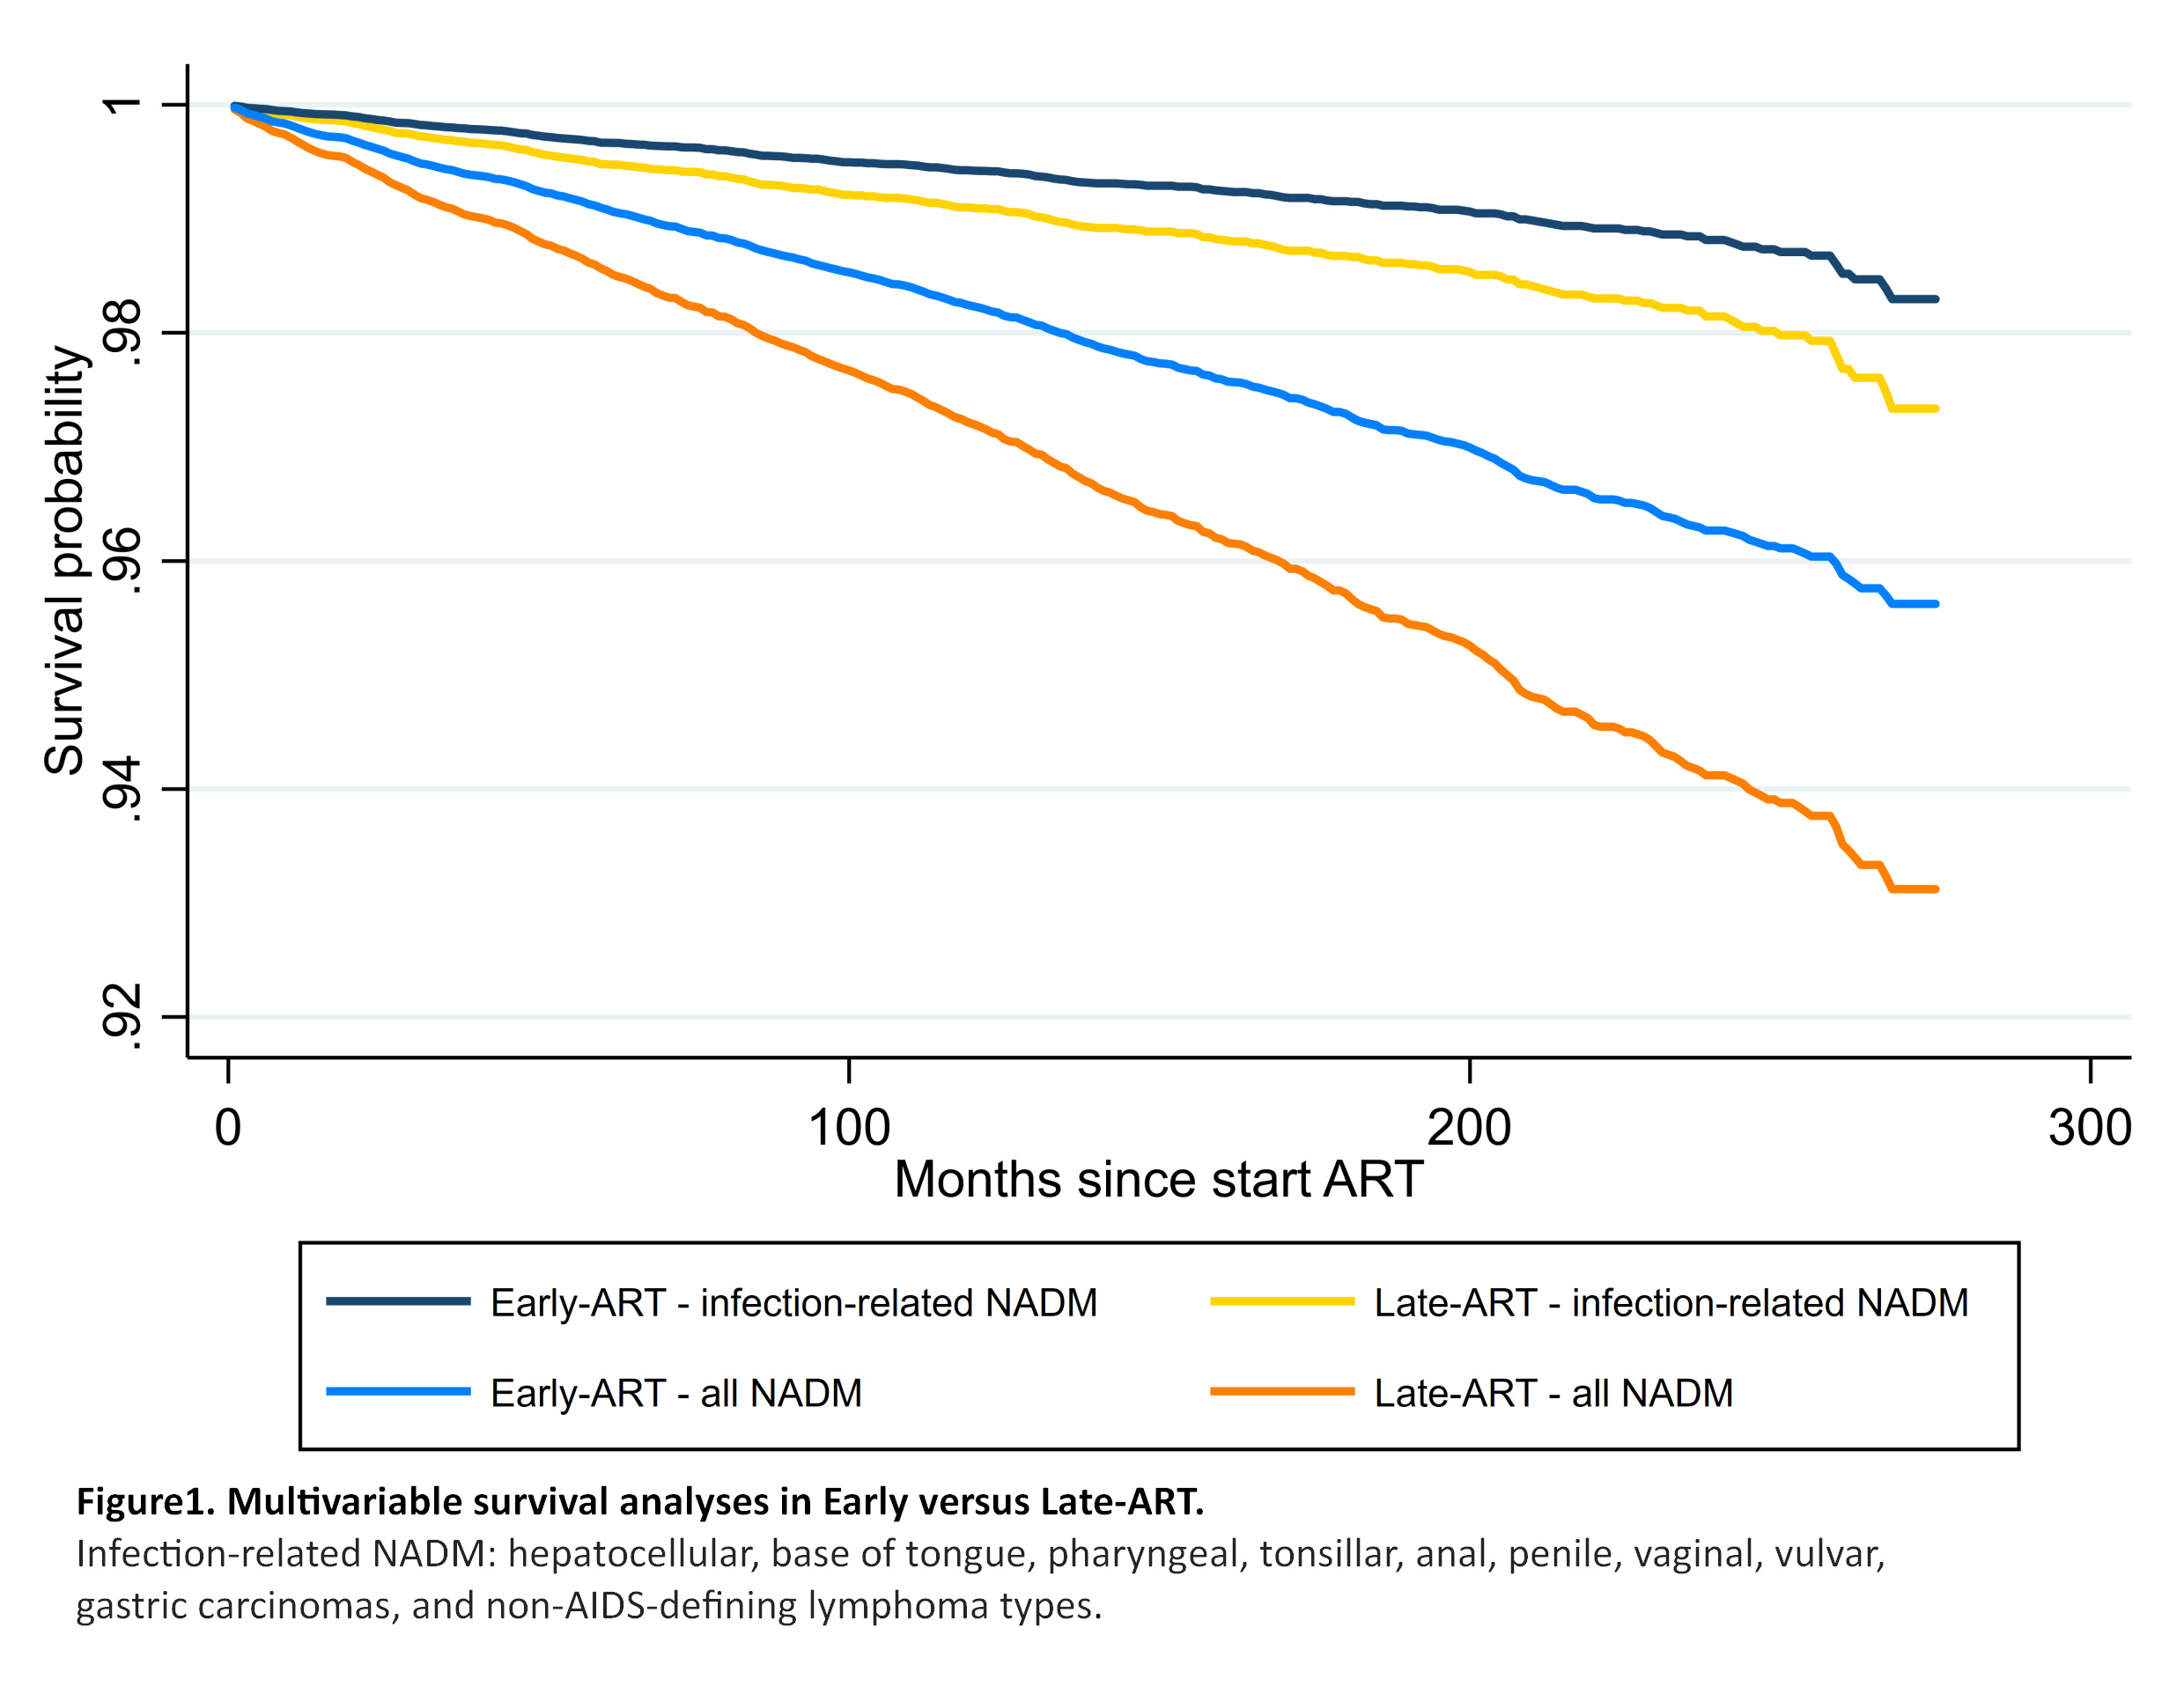
Early-ART compared to Late-ART starters were younger (median age 34.7 vs. 39.4 years), more often male (94.3 vs. 80.0%), with a CD4 count >500 cells/mm3 at ART start (42.6 vs. 18.8%), less often current or former smokers (39.7 vs. 44.9%), and had shorter median follow-up (68 vs. 115 months). In the Early-ART starters (n=2,036) 28 NADM occurred during 12,454 PYFU (IR 2.2/1000 PYFU) versus 1,160 NADM during 220,237 PYFU (IR 5.3/1000 PYFU) in Late-ART starters (n=22,183). Unadjusted, Early-ART start was associated with a significantly reduced NADM hazard (HR 0.48 [95% Confidence Interval (CI) 0.33–0.69]), which was only moderately attenuated after adjustment (multivariate HR 0.63 [95% CI 0.43–0.92]). When only considering infection-related NADM, 8 events occurred in Early-ART starters (n=2,037) during 12,531 PYFU (0.6/1000 PYFU) versus 378 during 223,390 PYFU (IR 1.7/1000 PYFU) in Late-ART starters (n=22,252). Early-ART start was associated with a significantly lower infection-related NADM hazard (HR 0.38 [95% CI 0.19–0.78]) in unadjusted analysis. In our multivariable model results were similar to the all-NADM analysis, but lacked statistical significance (HR 0.64 [95% CI 0.31–1.29]).
Conclusions:
Starting ART within a year of acquiring HIV or during primary infection reduces the risk of NADM compared to starting ART later after infection. Larger studies should assess the impact on individual NADM types.