Background:
People living with HIV (PLH) who have trouble maintaining adherence to 1st line regimens may develop virological failure requiring a regimen switch, but continued poor adherence remains a challenge. We assessed 2nd line treatment outcomes in the Thai National AIDS Program (NAP).
Methods:
PLH aged ≥ 18 years starting 1st line (non-nucleoside reverse transcriptase inhibitor-based) ART from 2008 to 2019, who subsequently switched to 2nd-line protease-inhibitor (PI)-based ART after virological failure were studied. Virological failure (VF) after 2nd-line switch was defined as viral load ≥1000 copies/mL, two consecutive times after switch. Competing risks regression was used to calculate the VF cumulative incidence, and sub-distribution hazard ratios (SHR), for associations between individual characteristics and VF, with lost to follow-up (LTFU) and death as competing events. LTFU was defined as not attending clinic >12 months; mortality was confirmed by National death registry linkage.
Results:
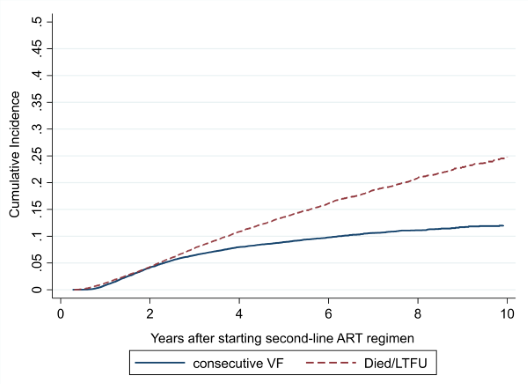
Of 299,261 people initiating ART, 29,061 (9.7%) switched to a 2nd line regimen after 1st line failure. Most (61%) were male with median age of 37 (IQR 31-44) years, median switch CD4 cell count of 149 (IQR 49-300) cells/mm3 and median 1st line ART duration of 3.6 (IQR 1.8-5.8) years. 2nd line regimens were ritonavir booster lopinavir (LPV/r) (96%), atazanavir (2%) or darunavir (DRV/r) (2%). Overall attrition after 2nd-line switch was death: 4,606 (16%) and LTFU: 5,316 (18%). The cumulative incidence of VF in 25,696 PLH with viral load testing after switch was 0.85% (95% CI 0.74-0.97%), 4.15% (95% CI 3.90-4.41%), 7.96% (95% CI 7.60-8.34%) and 12.10 (95% CI 11.42-12.74), at 1, 2, 4 and 10 years, respectively (Figure). VF was more common in females (aSHR 1.70 (95% CI 1.56- 1.86)), younger PLH (aSHR in those aged 18 to < 25 years 2.84 (95% CI 2.33-3.47 vs >50 years)), and lower time-updated CD4 cell count. Compared to those with CD4 ≥350 cells/mm3, the aSHR 10.35 (95% CI 9.29-11.53) in those with CD4 < 200 and 3.25 (95% CI 2.83-3.73) in those with CD4 200 - < 350. VF in those taking DRV/r was less likely compared to LPV/r-based regimens.
Conclusions:
VF rate after switching to 2nd line PI-based regimens was approximately 12% at 10 years, but rates of death and LTFU were high. VF switch was more common in younger adults and females, possibly due to non-adherence/intolerance to LPV/r. A multidisciplinary support system is needed for this population.
Cumulative incidence of second-line ART regimen failure (consecutive VF)