Background:
Chronic lung disease is an increasingly important comorbidity for persons aging with HIV. Persons with HIV(PWH) can experience accelerated decline in lung function, including spirometry measures(FEV1). The current implications of this lung function decline on all cause and HIV-related mortality warrants further investigation. Additionally, the normalized FEV1Q has recently been developed to improve interpretation of lung function without biases related to sex or race but has not yet been studied in cohorts of PWH. We leveraged the AIDS Linked to the Intravenous Experience(ALIVE) cohort in Baltimore, MD, consisting of PWH and matched HIV-uninfected participants, to study the implications of impaired lung function in a high-risk HIV cohort.
Methods:
We analyzed 2009-2019 ALIVE participant data. Lung function(FEV1 and FEV1Q) and clinical data(HIV RNA, comorbidity data) were collected at semi-annual visits. Mortality was derived from the national death index and clinical records, assessing all-cause and mortality due to HIV and chronic disease. Associations between time-updated lung function and mortality were analyzed in cox-proportional hazard models, adjusted for demographics, smoking(pack-years and status), injection drug use(IDU), HIV status, and comorbidity index. Models were also stratified by HIV status with adjustment for viremic control(<400copies/ml).
Results:
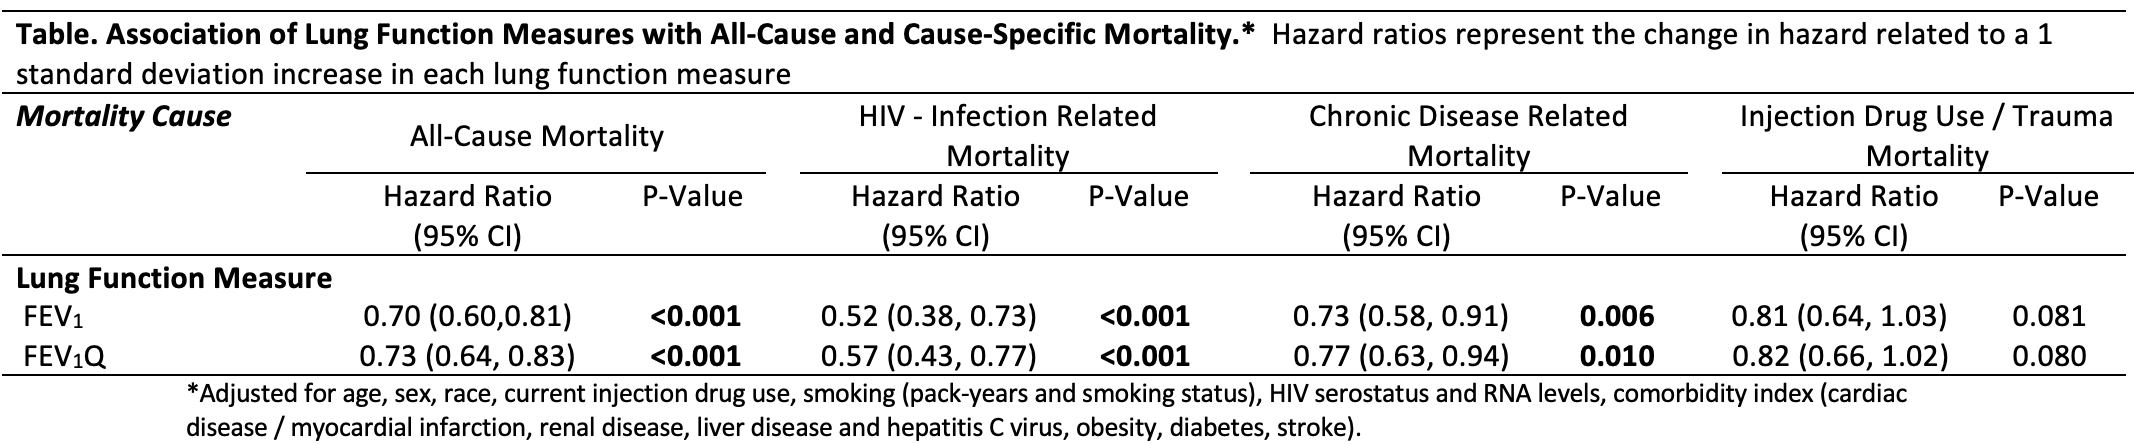
1534 participants(474 PWH) contributed 10515 lung function measures over 10 years. Mean age at entry was 50, with 34% reporting active IDU and 84% current smokers. Among PWH, 53% had detectable HIV RNA. Mortality was high with 410(26%) deaths during the study period; 35% among PWH. In adjusted models, accounting for comorbidities and risk factors, a 1SD increase in FEV1 (HR 0.70; P<0.01) and FEV1Q (HR 0.73; P<0.01) was associated with lower all-cause mortality. Higher lung function was protective for HIV-related mortality (FEV1, HR 0.52, P<0.01; FEV1Q, HR 0.57, P<0.01). Among PWH, after adjusting for viremic control, lung function remained associated with all cause(HR 0.62; P<0.01) and HIV-related mortality(HR 0.54; P<0.01).
Conclusions:
We demonstrate that in a high-risk HIV cohort, after accounting for behavioral risk factors and comorbidities, lung function remains highly associated with all cause and HIV related mortality. These results are consistent when using the normalized FEV1Q, which may be less susceptible to bias. The results highlight the importance of lung disease and interventions to preserve lung health in PWH.