Background
UNAIDS models predict rises in worldwide annual HIV incidence from 1.3 million in 2024 to 2.9 million in 2027, with HIV-related deaths rising from 0.6 to 1.8 million in 2027, due to decreased donor support. Long-Acting (LA) PrEP with cabotegravir (CAB-LA) or lenacapavir (LEN) show superior protection from HIV acquisition versus oral TDF/FTC. CAB-LA is available for PrEP, at annual prices of US $22,000 in the US, versus $200/year in sub-Saharan Africa. Lenacapavir was launched in the US for $28,000/year, but sold in Africa for $60/year, with an estimated cost price of $25/year.
Methods
The UNAIDS Spectrum model was used to estimate HIV incidence in countries included/excluded from voluntary licenses for LEN and CAB-LA. Worldwide sales of CAB-LA in 2024 were combined with efficacy from HPTN 083/4 and background HIV risk in the PURPOSE trials to estimate HIV acquisitions prevented in 2024, in the US, Europe and LMICs included the voluntary license (VL). In the US, annual sales were combined with 35% discounted prices (US $14,000/year). For LMICs in the CAB-LA VL, annual price of US $200/year was assumed based on recent data.
Results
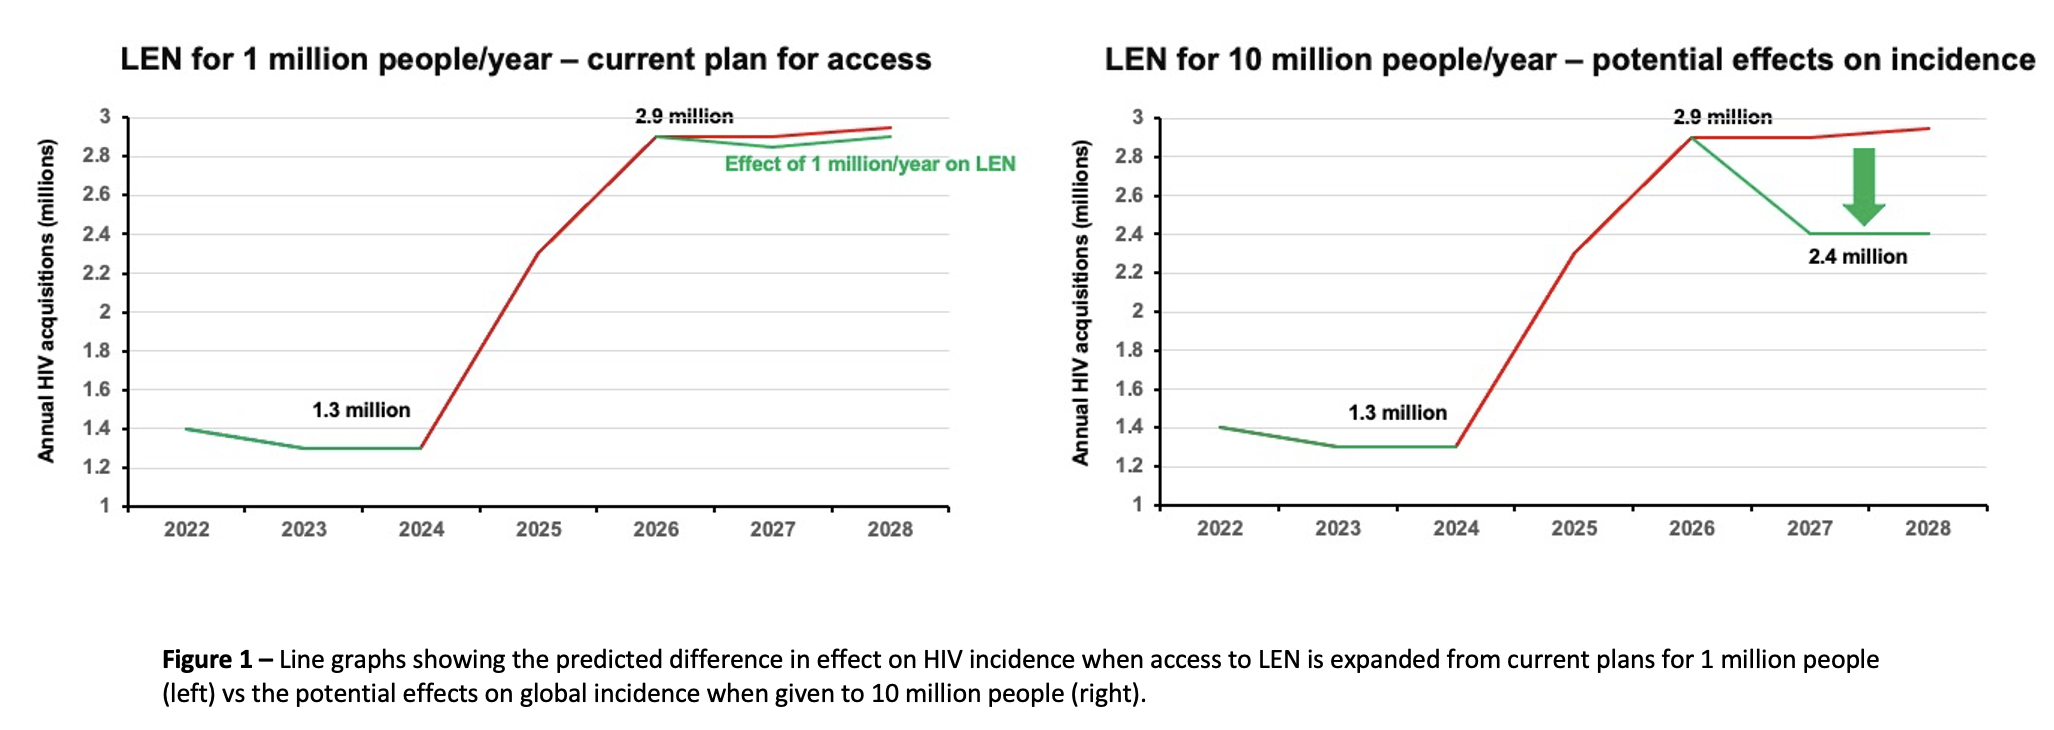
In 2024, CAB-LA sales were $270 million in the US, $9 million in LMICs and <$1 million in Europe. For US, $270 million of sales would supply 19,000 people. Assuming similar background HIV incidence to the PURPOSE trials, this could have prevented 443 new HIV acquisitions in the US in 2024 of the total 32,000 estimated (1.4%). In LMICs, $9 million in sales would have supplied approximately 55,000 people, potentially preventing 1,430 of the 921,000 HIV acquisitions in eligible countries (0.2%). Current supplies of LEN from PEPFAR/GFATM could supply 1 million people by 2027. However, based on background HIV incidence in the PURPOSE trials and projected rises after US funding cuts, this would only prevent 50,000 new HIV acquisitions/year. At least 10 million people would need to take LEN in LMICs to lower HIV acquisitions by 500,000/year (17% of projected 2028 total of 2.9 million).
Conclusions
Current access plans for LA PrEP will have an insignificant impact on HIV incidence, both in HICs and in LMICs. High prices in the US and Europe are preventing widespread reimbursement. Prices below $1000/year will be needed for LEN or CAB-LA to be used instead of oral PrEP in high income countries. In LMICs, at least 10 million people will need to take LA PrEP to have significant effects on new HIV acquisitions.
Table or Figure