Background
Disseminated TB is a common cause of hospitalisation for people with HIV and has high early mortality.
Methods
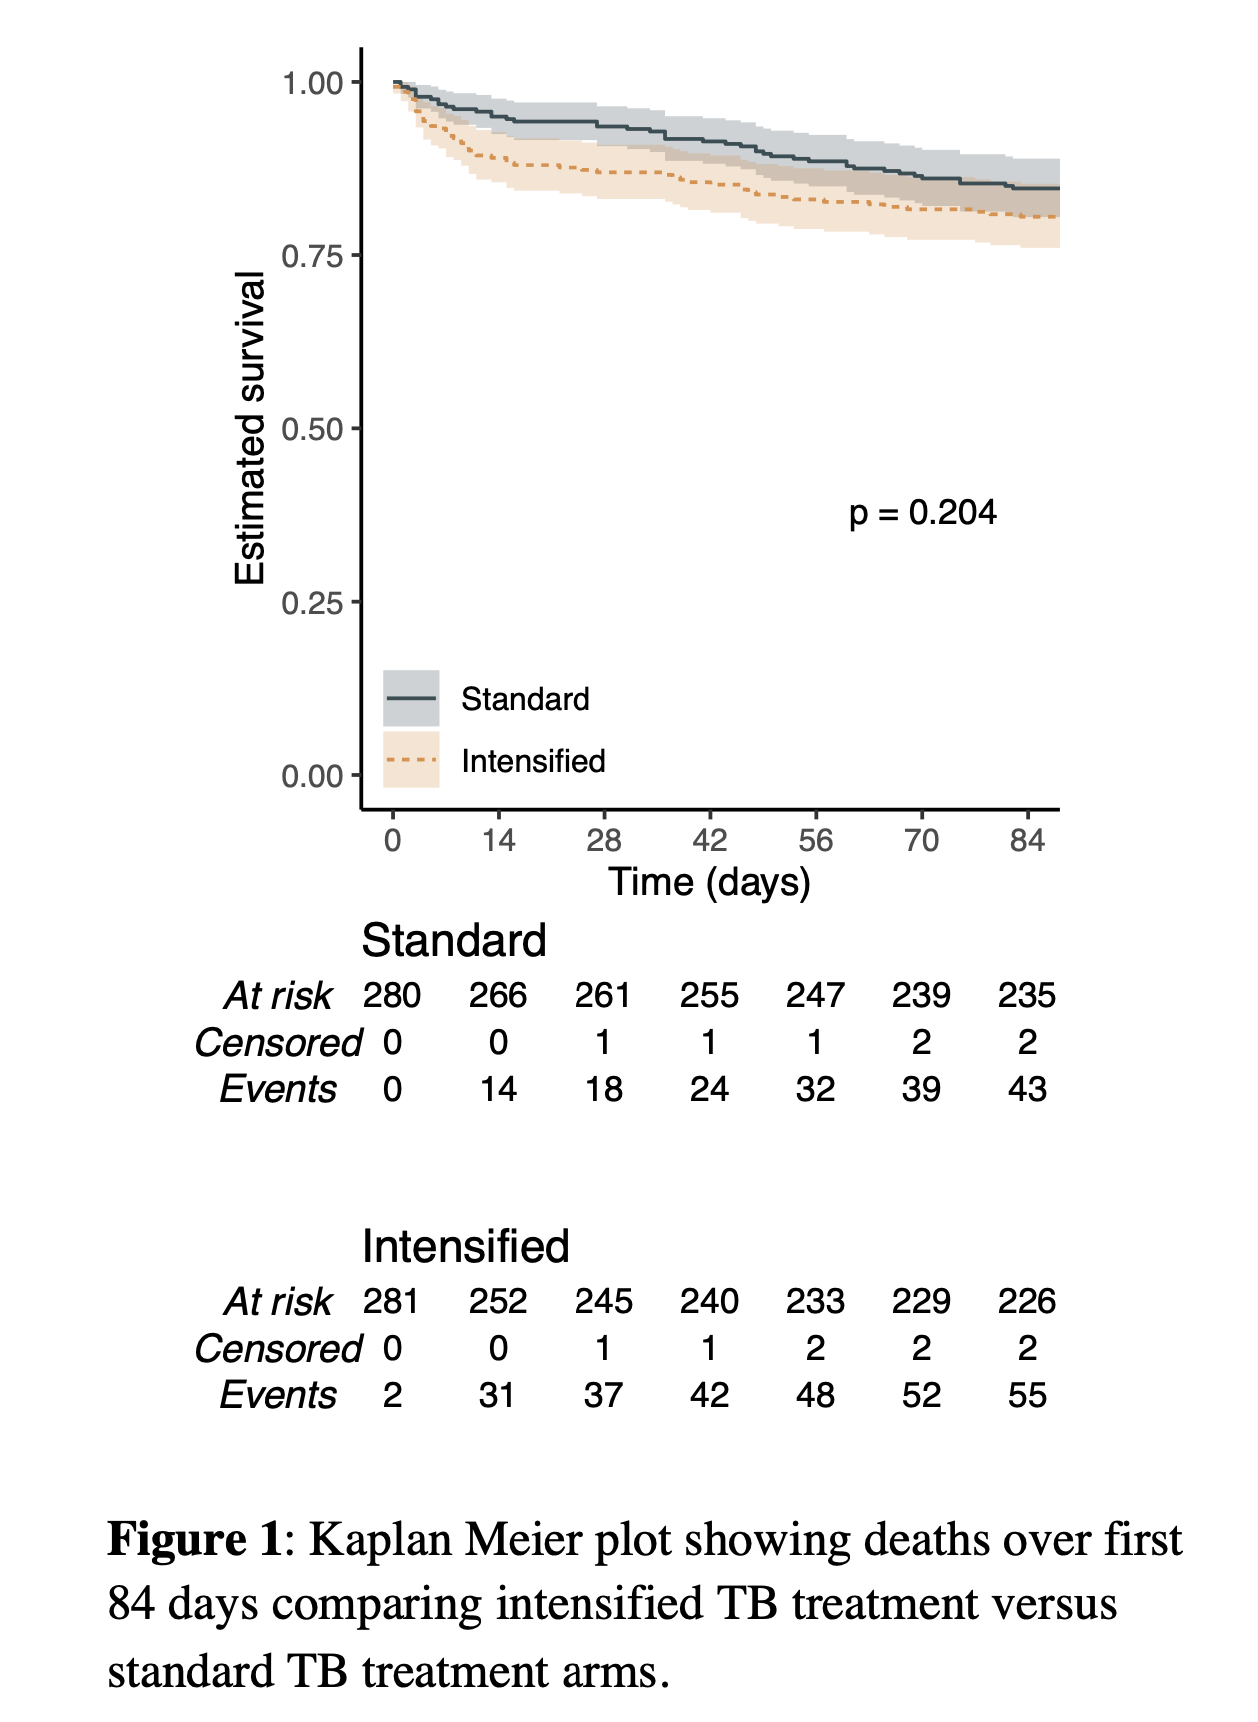
The NEW STRAT-TB trial, conducted at 3 hospitals in Cape Town, South Africa, has a 2×2 factorial randomization to standard TB treatment versus intensified TB treatment (standard TB treatment with rifampicin dose increased to 35mg/kg/d plus levofloxacin) and prednisone (1.5mg/kg/d) versus identical placebo, for the initial 14 days, followed by standard TB treatment. Adults admitted to hospital with HIV-associated disseminated TB (one or more of urine Alere LAM, urine Xpert Ultra or blood Xpert Ultra positive) are eligible. The primary endpoint is 12-week mortality. The absolute difference between arms was estimated using the Kaplan-Meier method with bootstrapping to obtain 95% confidence intervals and associated p-values.
Results
On 6 June 2024, the intensified TB treatment arm was stopped by the DSMB due to higher 2-week mortality. Investigators remain blinded to prednisone versus placebo allocation. 580 participants (of planned 732) had been enrolled with 563 in mITT population. Median age was 36 years (interquartile range, IQR=30-43), 299 (53%) were female with median CD4 count 42 cells/μL (IQR=18-92), Hb 8.2 g/dL (IQR=6.9-9.6), venous lactate 2.1 mmol/L (IQR=1.6-2.9) and creatinine 70μmol/L (IQR=52-102). 113 (20%) had eGFR < 50mL/min. 83%, 67% and 31% were positive by urine Xpert Ultra, urine Alere LAM and blood Xpert Ultra, respectively. 55/548 participants (10%) had HIV RNA < 50 copies/mL. 14-day mortality was 31/283 (11.0%) in the intensified arm and 14/280 (5.0%) in the standard arm (difference 6.0%; 95%CI 1.6% – 10.4%; p=0.008). Mortality at 12 weeks was 55/283 (19.4%) in the intensified arm and 43/280 (15.4%) in the standard arm (difference 4.1%; 95%CI -2.2% – 10.4%; p=0.204). None of the early deaths were attributed to drug-induced liver injury. Clinical hepatitis events within 14 days occurred in 15 participants in the intensified arm and 21 in the standard arm.
Conclusions
Intensified TB treatment was associated with higher 2-week mortality, which has not been observed in prior trials of higher dose rifamycins and fluoroquinolones in TB. Reasons for higher 2-week mortality are currently unclear. Interaction with prednisone will be explored when that randomization is unblinded. Strategies involving higher dose rifamycins and fluoroquinolones should be used with caution in critically ill inpatients with HIV and disseminated TB.
Table or Figure