Background
Tuberculosis (TB) remains a leading cause of hospitalization and death among people living with HIV (PLHIV), notably in those with advanced HIV disease.
Methods
DATURA (ANRS 12424) was a randomized open-label trial conducted in Cambodia, Cameroon, Guinea, Mozambique, Uganda and Zambia. PLHIV aged 15 years or older, hospitalized for TB with CD4≤100 cells/µL, were randomly assigned to receive either increased doses of rifampicin (35 mg/kg/d) and isoniazid (10 mg/kg/d) with standard doses of ethambutol and pyrazinamide for the first 8 weeks, together with oral corticosteroids for 6 weeks (intervention arm), or standard TB treatment (comparative arm). Primary outcome was death occurring within 48 weeks (end of follow-up). Treatment effects were estimated with Cox proportional hazards model for mortality and a log-binomial model for grade 3-4 adverse events (AE). Participants who received at least one dose of TB treatment defined the modified intention-to-treat (mITT) population.
Results
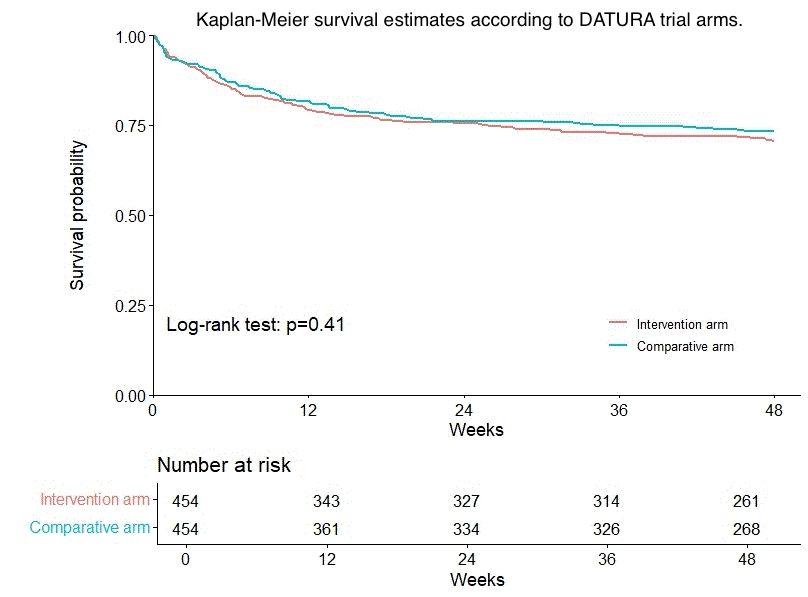
Between April 2022 and December 2024, 911 participants were randomized and 908 were analyzed (454 per arm: mITT population). At baseline, 44% of participants were women, with a median age of 37 years (IQR: 30-44), a median body mass index (BMI) of 17.6 kg/m2 (IQR: 15.6-19.7), incl. 271 (30%) with a BMI <16 kg/m2, a median hemoglobin of 9.0 g/dL (IQR: 7.4-10.5), and a median CD4 count of 44 cells/µL (IQR: 22-76), all well balanced between arms. TB diagnosis was based on a positive Xpert® MTB/RIF test in 70% of participants, a positive urine Determine™ TB LAM in 26% and a chest X-ray suggestive of TB in 4%. Overall, 801 (88%) participants had disseminated TB. At week 48, there were 129 (28%) deaths in the intervention arm and 119 (26%) in the comparative arm. Hazard ratio [95% confidence interval] for death was 1.13 [0.88-1.45] in the mITT population (adjusted on CD4 count and country), 1.11 [0.86-1.45] in participants with disseminated TB, 1.28 [0.94-1.75] in those with CD4≤50 cells/µL, 0.88 [0.58-1.34] in those with CD4>50 cells/µL, and 1.05 [0.77-1.44] for microbiologically confirmed TB. Overall, 324 participants in the intervention arm and 336 participants in the comparative arm experienced a grade 3-4 AE, with a relative risk of 0.97 [0.90-1.05].
Conclusions
Intensifying the initial phase of TB treatment did not decrease the risk of mortality in severely immunocompromised HIV-infected adults and adolescents. Tolerance did not differ between arms. Other strategies are needed to reduce this high mortality.
Table or Figure