Background
DTG/3TC is approved for initial therapy regardless of baseline (BL) HIV-1 RNA (VL) and CD4+ count; however, treatment guidelines restrict use to those with BL VL <500,000 c/mL. Efficacy and safety of DTG/3TC (2DR) was compared to DTG-based 3-drug regimens (3DR) among ART-naive participants with high BL VLs and low CD4+ counts in a meta-analysis of prospective trials.
Methods
GEMINI-1/-2, STAT, DOLCE, and D2ARLING Phase III/IV clinical trial data were analyzed with BL VL and CD4+ as continuous covariates. The proportions achieving VL <50 c/mL at (W)eek 48 (FDA Snapshot algorithm) between 2DR vs. 3DR were compared. Bayesian hierarchical logistic-regression with g-computation analysis was used to estimate treatment differences with 95% credible intervals (CrI) generated. Density-weighted estimates were calculated to summarize the average risk difference (RD) of 3DR-2DR in viral suppression. Rate of confirmed virologic withdrawal (CVW), drug-emergent resistance, drug-related adverse events (AEs), and AE-related treatment withdrawals were also evaluated.
Results
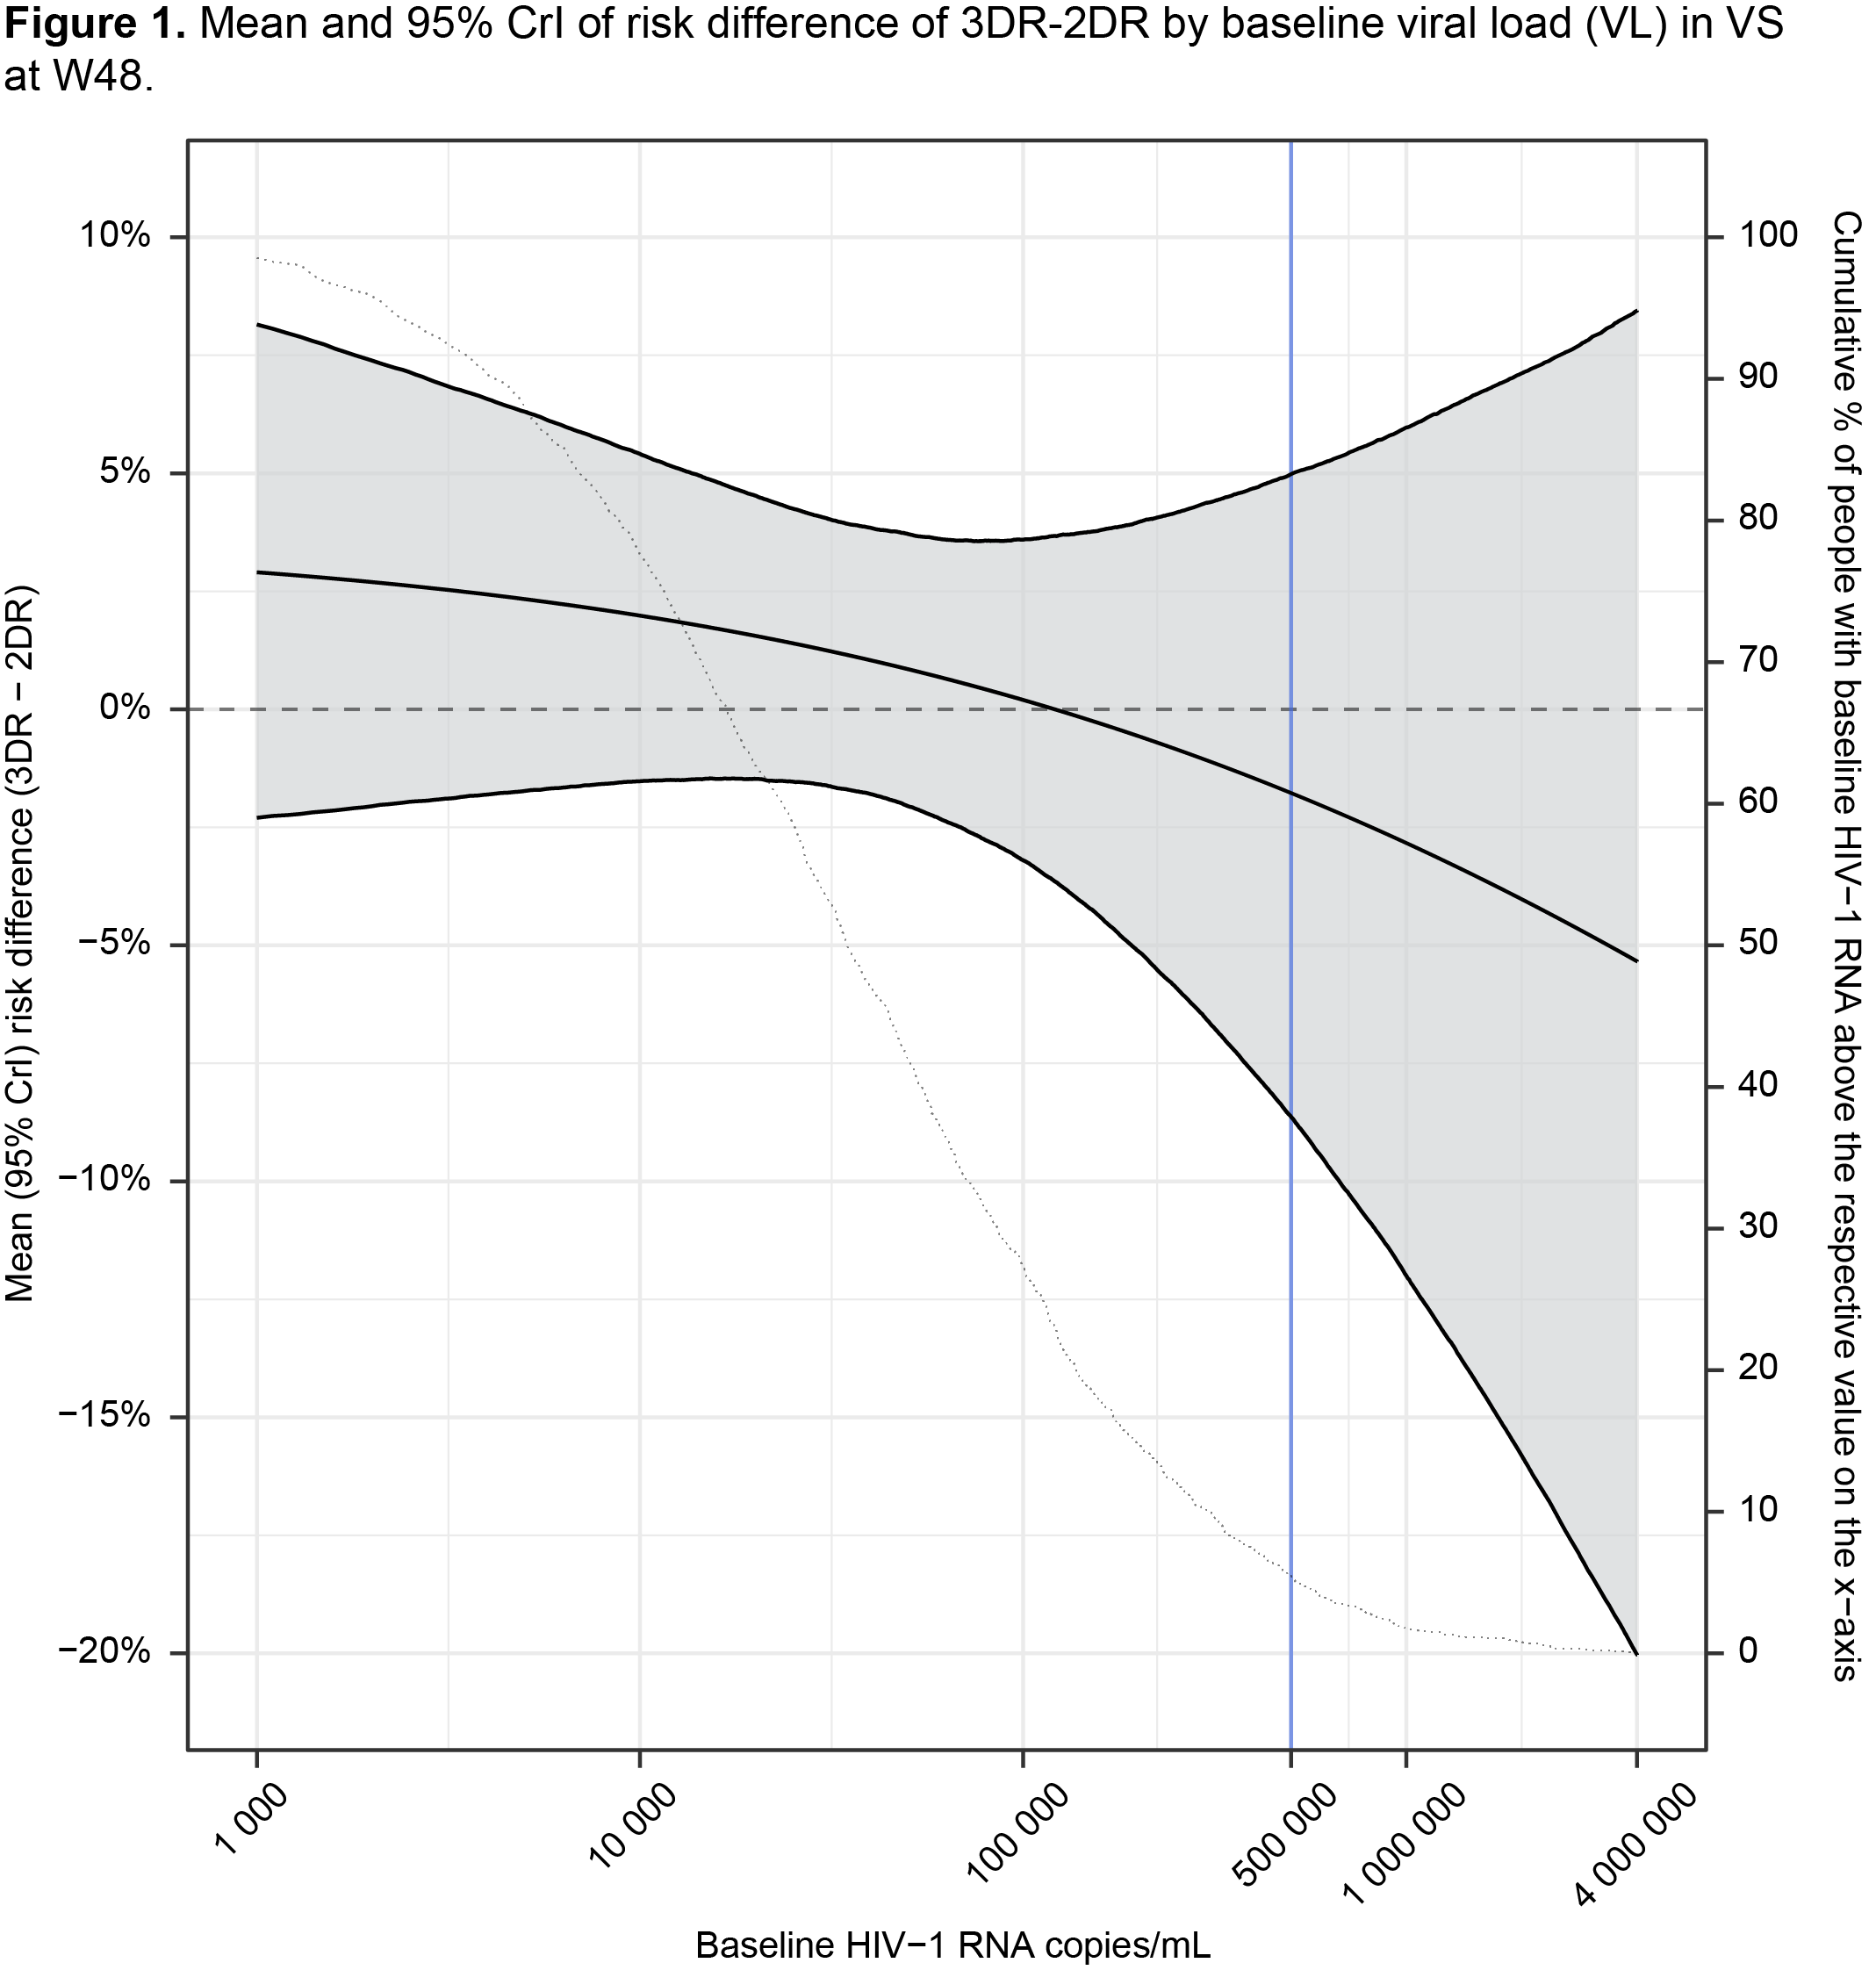
Among 1856 participants analyzed, the study population was generally well-balanced with median age of 33y, 17% female, 13.5% Black race. Overall, 113 (6%) had BL VL ≥500K c/mL and 41 (2%) had BL VL ≥1M c/mL; 812 (43%) had BL CD4+ <350 cells/mm3 and 368 (20%) had BL CD4+ <200 cells/mm3. Figure 1 shows the mean and 95% CrI with RD at W48 by BL VL, with dotted line showing the percentage of the population above the VL on the x-axis. For BL VL ≥500K c/mL, estimated response rates were 86.7% for DTG/3TC vs. 84.4% for DTG/TDF/XTC [RD (95% CrI) -2.3% (-10.2%, 5.4%)]. For BL CD4+ <200 cells/mm3, they were 86.3% for DTG/3TC vs. 90.1% for DTG/TDF/XTC [RD (95% CrI) 3.7% (-1.3%, 8.6%)]. CVWs and treatment-emergent resistance were rare through W48. Both regimens showed good tolerability with no notable differences between groups.
Conclusions
DTG/3TC was estimated to have comparable efficacy to DTG-based 3DRs at W48 in ART-naive participants across all BL VLs and CD4+ categories with 95% CrIs containing zero, including VL ≥500K c/mL and CD4+ <200 cells/mm3, providing no plausible evidence of treatment differences. CVWs and treatment-emergent resistance were rare. These findings support the potential revision of HIV treatment guidelines to recommend DTG/3TC in ART-naive individuals with high BL VLs and low CD4+ counts.
Table or Figure