Background
Cytomegalovirus (CMV) infection is common among people with HIV (PWH) and may contribute to immune activation and inflammation, which could hinder immune recovery with antiretroviral therapy (ART). Within the Southern Alberta HIV Clinic (SAC) in Calgary Canada, we aimed to identify the seroprevalence of CMV and its association with CD4 T-cell and CD4/CD8 ratio recovery among PWH who maintain HIV viral suppression.
Methods
PWH 18 years or older accessing care at SAC between 01/01/1998-01/06/2022 with at least one CMV serologic test and initiated on ART were included at the first HIV viral load result of <200 copies/mL (study entry). Study exit was defined as the first date the patient reached the study outcome [CD4 cell count of >499 cells/mm3 (model 1) or CD4/CD8 ratio >1 (model 2)], had a viral load measurement of >200 copies/mL (as a proxy for ART adherence), lost-to follow up, death, or 01/06/2022. PWH were excluded if they had <2 measurements for CD4 or CD4/CD8 ratio during the study period. Continuous time-to-event Cox proportional hazard models estimated crude and adjusted hazards ratios (aHR) and 95% confidence intervals for CD4 count recovery to >499 cells/mm3 and CD4/CD8 ratio of >1 at 10 years by CMV serostatus. Models were adjusted for calendar year, age, sex, race/ethnicity, HIV acquisition risk, HCV, HBV, renal disease, diabetes, cardiovascular disease, and CD4 nadir. 10-year cumulative incidence of CD4 and CD4/CD8 ratio recovery by CMV serostatus was estimated using Kaplan-Meier methods.
Results
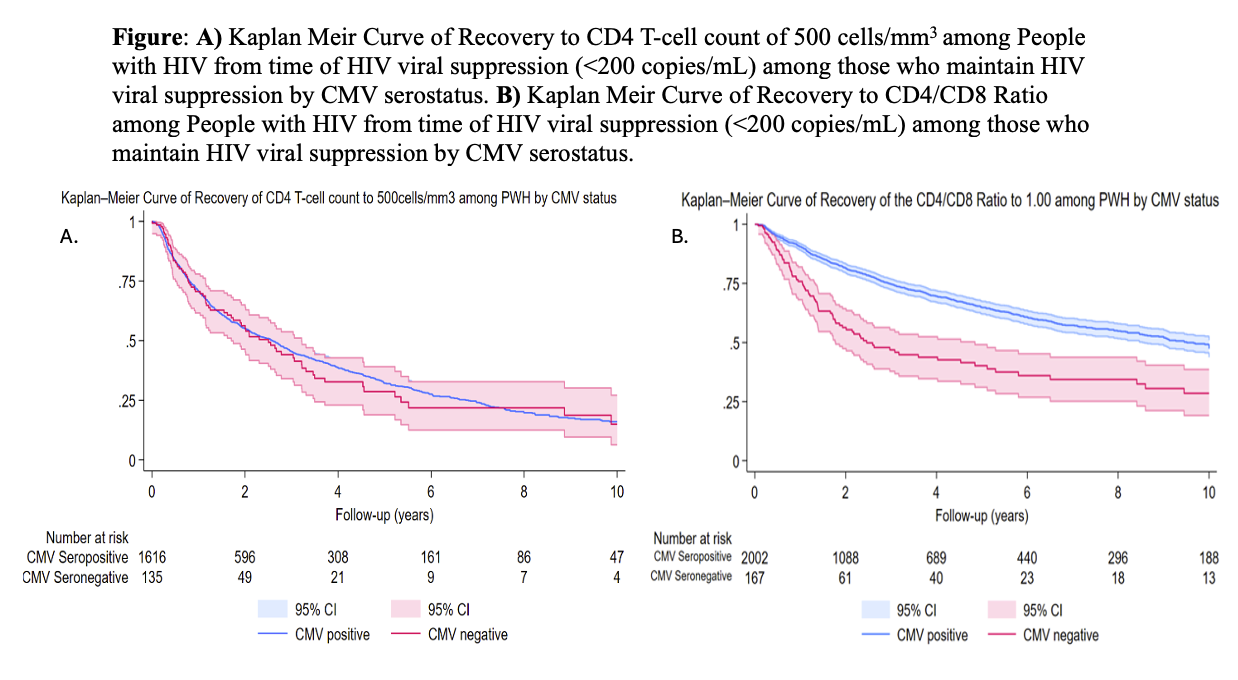
Among 2,538 PWH, 2,310 (91%) were CMV seropositive, 787 (31%) had initial CD4 counts of >499 cells/mm3 and 369 (15%) had initial CD4/CD8 ratios >1 and were excluded from the analyses. Over 10 years, 84% of CMV seropositive and 85% of CMV seronegative PWH achieved a CD4 count of >499 cells/mm3 and 53% of CMV seropositive and 72% of CMV seronegative PWH achieved a CD4/CD8 ratio of >1 (figure). CMV seronegativity was not associated with CD4 recovery to 500 cells/mm3 (aHR 1.08 [0.84-1.40]), however, was associated with a greater likelihood of a CD4/CD8 ratio of >1 (aHR 2.32 [1.80-3.00]) at 10-years of follow-up.
Conclusions
CMV coinfection is common among PWH. CMV is associated with a reduced CD4/CD8 ratio recovery, however, not with CD4 T-cell recovery among PWH who maintain HIV viral suppression. This suggests CMV may contribute to chronic infection-mediated immune activation and inflammation among PWH.
Table or Figure