Background
Twelve weeks of weekly rifapentine and isoniazid (3HP) effectively prevents TB in children, including children with HIV (CLHIV). In adults, 3HP can be co-administered with once-daily dolutegravir (DTG) + 2 NRTIs without dose adjustment. However, CLHIV clear DTG faster and may require twice-daily dosing to mitigate the induction effect of rifapentine and maintain adequate exposures, which poses implementation challenges. We conducted a two-stage phase I/II study to evaluate DTG pharmacokinetics (PK), safety and virologic suppression in CLHIV taking DTG with 3HP. In Stage 1, CLHIV received twice-daily DTG; PK modeling projected that once-daily DTG would produce therapeutic concentrations in CLHIV ≥10kg. In Stage 2, once-daily DTG was tested and the results are presented here.
Methods
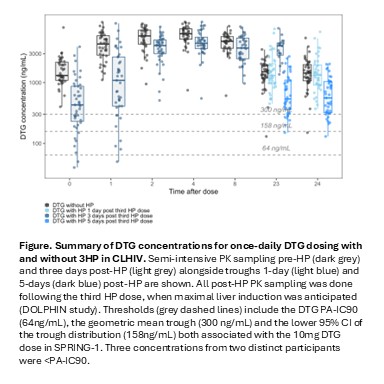
CLHIV ≥10kg with suppressed viral loads (<50 copies/mL) were enrolled and received once-daily DTG + 2 NRTIs, started ≥4 weeks before 3HP. Semi-intensive DTG PK sampling was performed prior to 3HP and 3 days after the third HP dose with additional troughs 1- and 5-days post-dose. HIV-1 RNA was measured at baseline, HP week 3, and study completion. The primary endpoint was DTG PK and secondary endpoints were safety and viral suppression. Target DTG PK parameters with HP were acceptable if the lower 95% CI of the observed trough was >158 ng/mL and all troughs were >PA-IC90 (64 ng/mL).
Results
Of 41 participants enrolled, one withdrew; 19 (46%) were female and all were black African. Median age was 5.5 years (range 1.5-16.9). Mean CD4 count was 1090 cells/uL (sd 338) and 35% (sd 8%) in participants aged ≥6 years and <6 years, respectively. Nine (22%) participants had adherence <90% by pill count during HP. The lower 95% CI of the observed trough for once-daily DTG with HP was 200 ng/mL (overall) and 72 ng/mL (3 days post-dose). Two participants had pre-dose troughs <64 ng/mL 3 days post-dose (Figure), none were below the limit of quantification. There were no grade ≥3 treatment-related adverse events. Most participants (95%) remained virally suppressed throughout the study, and two had HIV-1 RNA blips (160 and 2,310 copies/mL) that resuppressed after adherence counseling.
Conclusions
Co-administration of DTG and HP was safe and well-tolerated. All participants were virologically suppressed at study completion despite two participants’ concentrations being below the PA-IC90. 3HP may be co-administered with DTG + 2 NRTIs in CLHIV ≥10kg without DTG dose adjustment together with strong adherence counseling.
Table or Figure