Background
Youth with HIV (YHIV) aged 15-24 years in South Africa (SA) experience challenges adhering to daily oral antiretroviral therapy (ART) compared to older people with HIV, leading to substantial short- and long-term morbidity and mortality. Long-acting injectable cabotegravir/rilpivirine (CAB/RPV) could reduce adherence barriers but is not available for treatment outside research settings.
Methods
Using the CEPAC model, we simulate YHIV in SA in care and prescribed ART (All_AYA, n=224,000), including those with oral ART adherence challenges (Lo_Adh, n=20,000). We compare two strategies, SOC: standard-of-care oral tenofovir/lamivudine/dolutegravir (TLD) ART versus LA-ART: two-monthly CAB/RPV with transition to TLD if still on CAB/RPV at age 25. Key inputs, informed by published data, for All_AYA/Lo_Adh include age (mean 20.5 years), sex (70% female), mean CD4 count (447/152 cells/µL), baseline viremia (21/100%), mean ART adherence (% pills taken/month: 74/18%), 24-month retention (91/82%), 1st-line ART efficacy (SOC=95%, LA-ART=94-97%) and costs/year (oral ART=$30-280, CAB/RPV=$270, HIV-related care=$130-1,290). Outcomes include life expectancy (LE), costs, and incremental cost-effectiveness ratios (ICERs, $/life-year-saved [LYS], discounted 3%/year. We vary key inputs and willingness-to-pay thresholds (base case: 50% SA GDP [$3,010/LYS]) in sensitivity analyses.
Results
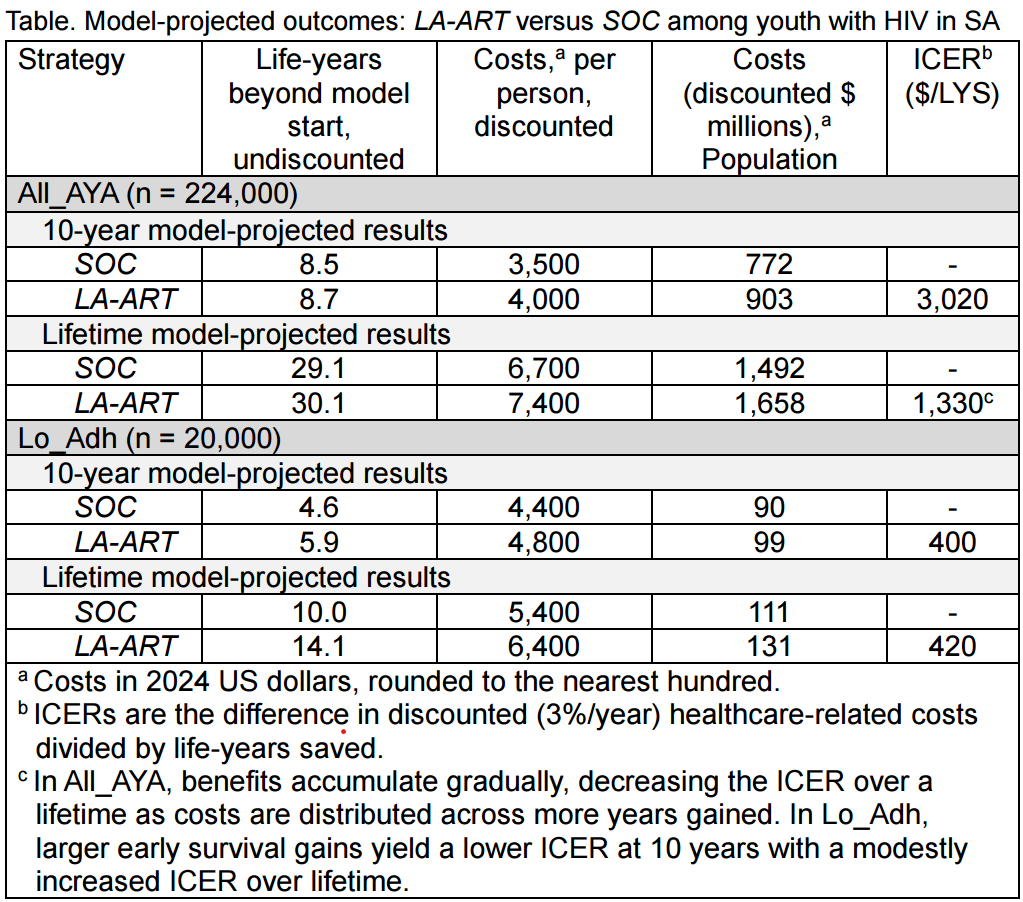
Over 10 years, LA-ART yielded modest gains in LE for All_AYA (8.7y in LA-ART vs 8.5y for SOC) but larger improvements in Lo_Adh (5.9y vs 4.6y, table). Over a lifetime, LA-ART would lead to greater LE than SOC in both cohorts (All_AYA: 30.1y vs 29.1y; Lo_Adh: 14.1y vs 10.0y), corresponding to 228,000 and 84,000 LYS at the population level. LA-ART’s ICER would be <$3,010/LYS in both cohorts (All_AYA=$1,330/LYS; Lo_Adh=$420/LYS) and would remain so at yearly drug prices ≤$580 for All_AYA and ≤$3,110 for Lo_Adh. CAB/RPV use regardless of age >25 further increased LE (All_AYA=30.8y; Lo_Adh=15.8y) and ICERs (All_AYA=$3,810/LYS; Lo_Adh=$740/LYS); for All_AYA, this would remain <$3,010/LYS only at drug prices ≤$220/year. In sensitivity analyses, cost-effectiveness was most sensitive to CAB/RPV price and efficacy.
Conclusions
Prioritizing access to LA ART during the critical developmental period of adolescence and young adulthood could markedly increase long-term survival for YHIV. Depending on pricing, LA ART could be cost-effective for South African YHIV, particularly those with adherence challenges.
Table or Figure