Background
Available data supporting global guidelines on the pharmacokinetics and safety of twice daily dolutegravir 10mg dispersible tablets (DT) in children 3-20kg with HIV and tuberculosis (TB) co-infection receiving rifampicin is scarce. We evaluated the pharmacokinetics and safety of twice daily dolutegravir 10mg DT in children 3-20kg on rifampicin.
Methods
We conducted an open-label, sequential non-randomised prospective study in children initiated on a rifampicin-based TB regimen who concurrently received weight-based dolutegravir 10mg dispersible tablets twice daily (BD) during TB treatment and once daily (OD) after stopping rifampicin (NCT04746547). Serial plasma samples were collected at steady-state during and after TB treatment and assayed using a validated LC-MS/MS method. Non-compartmental pharmacokinetic (PK) analyses were conducted using the ncappc package in R. Participants underwent regular clinical, viral load and safety monitoring.
Results
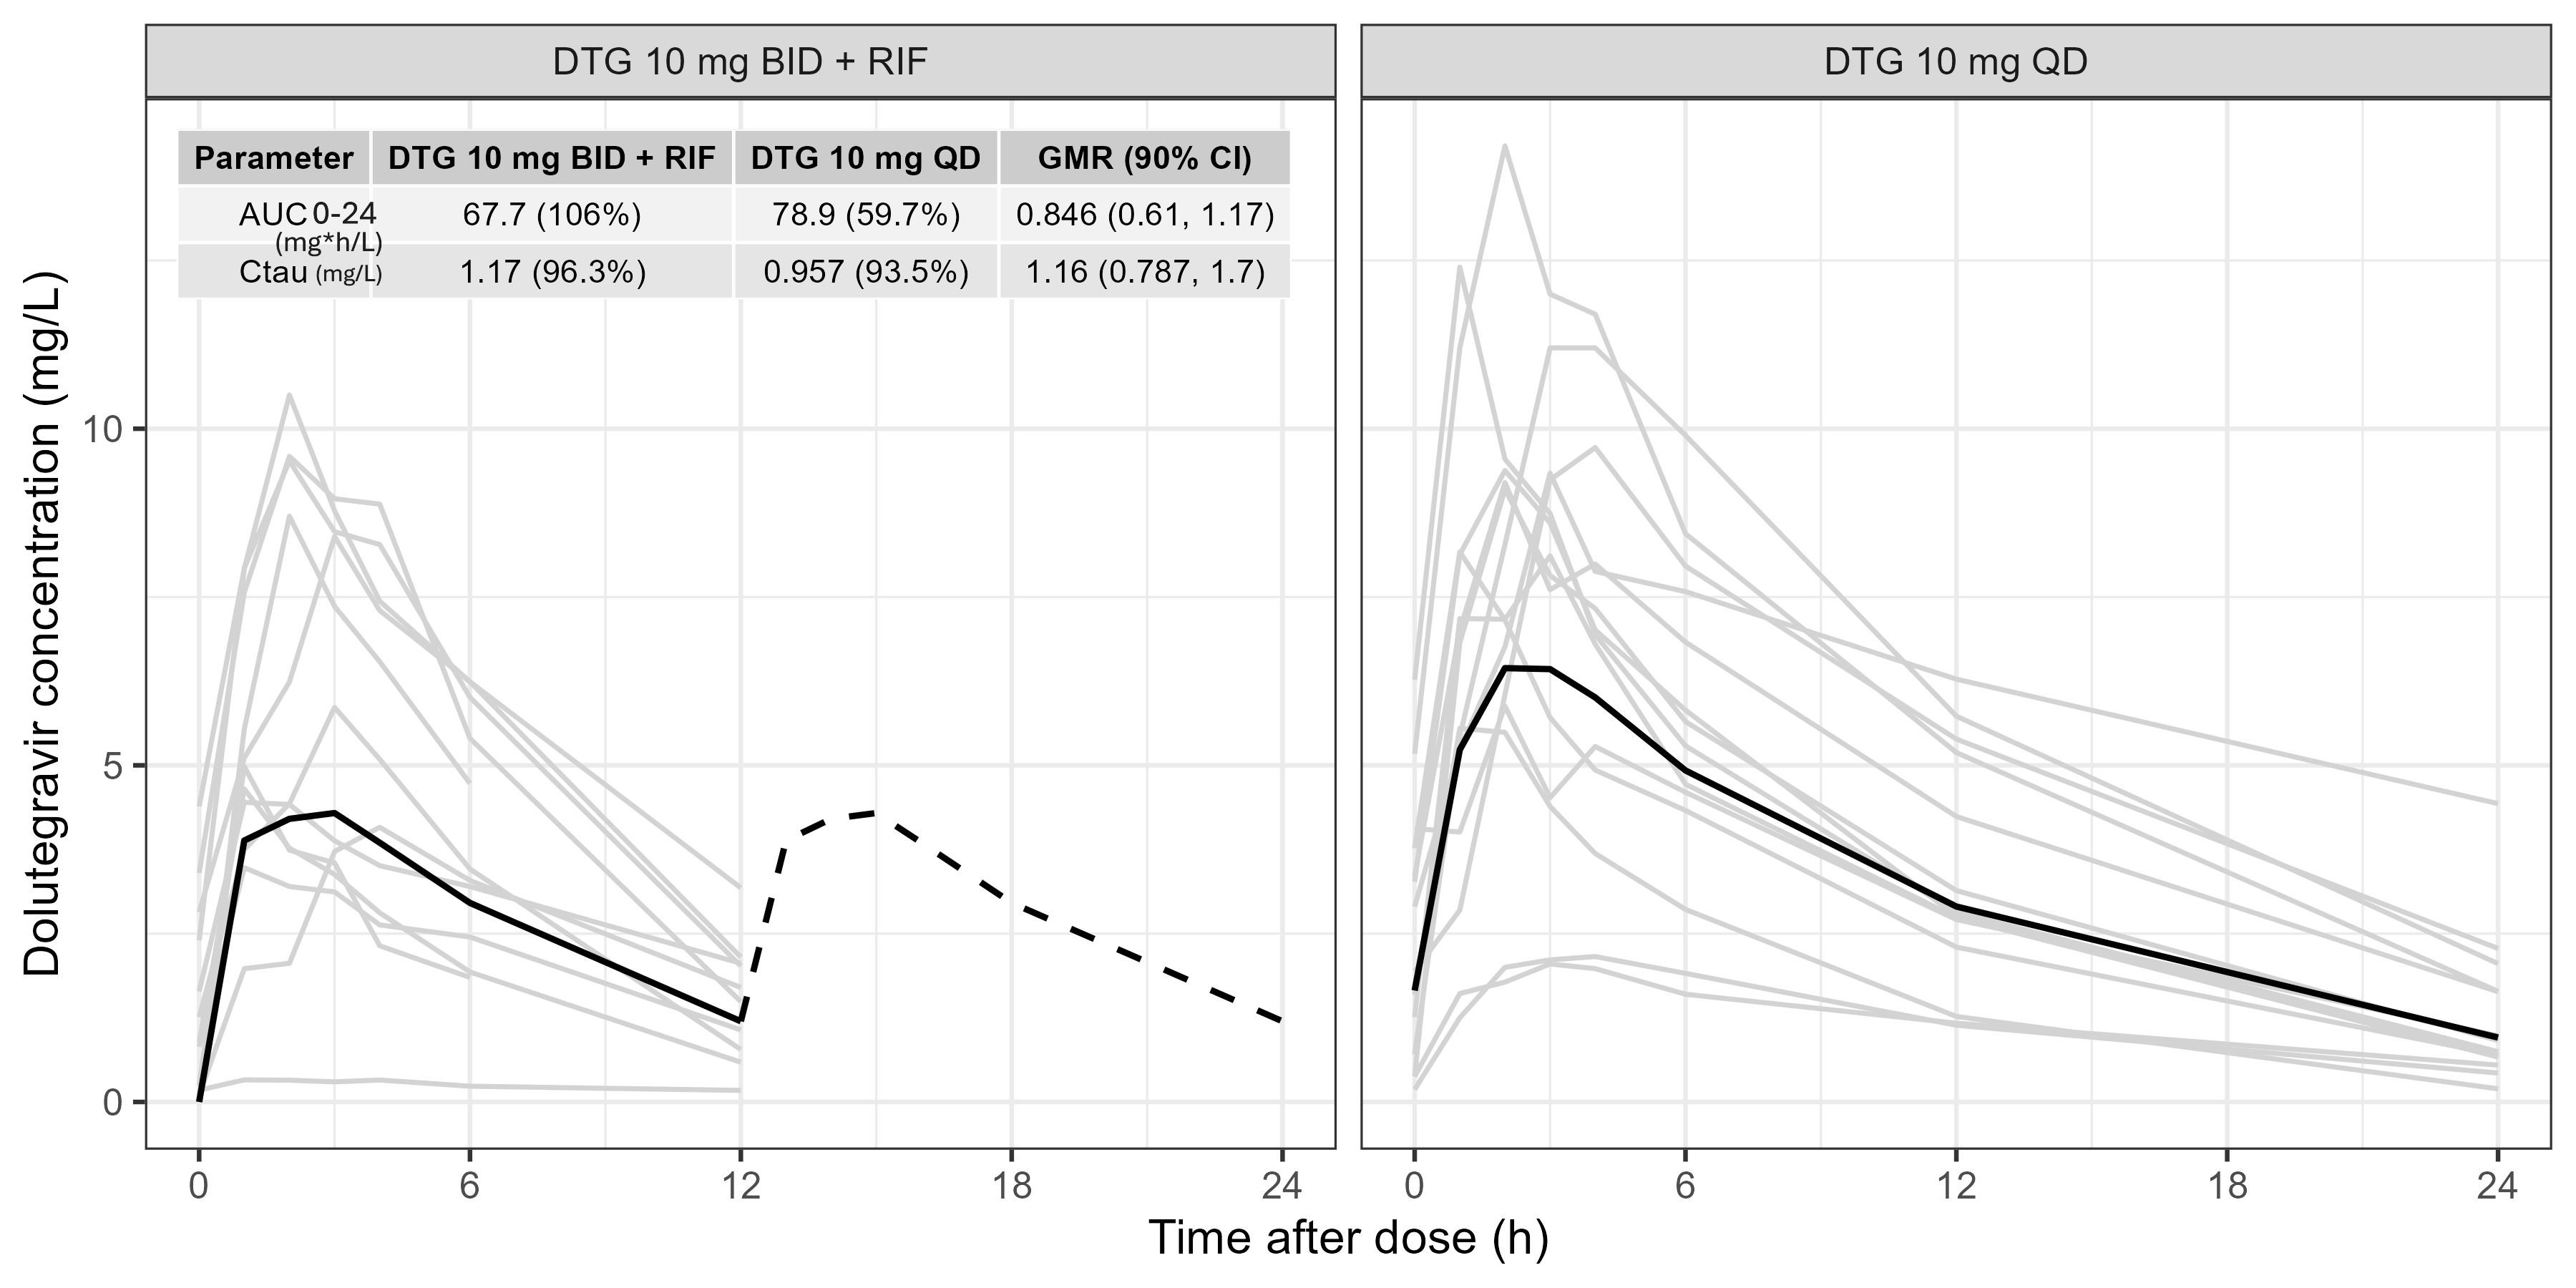
We enrolled 21 children between August 2023 and April 2025. Preliminary analysis of all data collected up to September 2025 showed Median (IQR) weight 9.8 (7.5-11.3); age 2.0 (1.0-3.0); 48% males; 100% black race in this cohort. The median (IQR) viral load and CD4 at baseline were 3.2 (2.4-4.3) log10-copies/mL and 1161.0 (652.0-1495.0) cells/μl. Data from 14 children were included in the preliminary PK analysis, contributing 14 profiles on twice daily dolutegravir plus rifampicin and 12 profiles on once daily dolutegravir (total of 334 dolutegravir plasma concentration values). Median trough concentration (CTau) was 1.60 and 0.829 mg/L, while AUC0-24 was 73.9 and 87.0 h*mg/L for participants on BID dolutegravir with rifampicin and OD dolutegravir, respectively. PK data are summarised in Figure 1. There were 14 grade 3 or higher adverse events and 9 SAEs, including one death, that were not related to study treatment. No treatment discontinuations due to AE’s were observed. Viral load suppression (<50 copies/mL) was achieved in 73% patients after six months of TB treatment.
Figure 1: Dolutegravir plasma concentration-time profiles during and after TB treatment.
Conclusions
Preliminary data from children 3-20kg receiving twice-daily dolutegravir during TB treatment suggest this dosing strategy is safe and achieves similar PK values to daily dolutegravir without rifampicin. These findings support the WHO and global guideline recommendations for dolutegravir 10mg DT dosing in children 3-20kg.
Table or Figure