Background
Aortic valve calcification (AVC), which shares a similar pathophysiology with atherosclerosis, has been linked to increased cardiovascular mortality. This study aimed to evaluate AVC progression in PLWH and its association with lipoprotein(a) [Lp(a)], a genetically determined risk factor for atherosclerosis, together with traditional cardiovascular risk factors in aging PLWH receiving long-term suppressive antiretroviral therapy (ART).
Methods
We enrolled Thai PLWH aged ≥50 years from HIV-NAT in Bangkok. Individuals with structural heart disease or bicuspid aortic valves were excluded by echocardiogram. Baseline assessments included demographics, comorbidities, 10-year ASCVD risk score, HIV viral load, CD4 count, ART regimen/duration, inflammatory markers, and statin use. Cardiac CT was performed at baseline (2015–2018) and repeated at follow-up (2023–2024). AVC progression was defined as a square-root difference in Agatston score >2.5. Stored sera were tested for Lp(a). Logistic regression assessed the association of elevated Lp(a) (>50 mg/dL) and other determinants with AVC progression and new AVC.
Results
Among 275 participants, 61 (22%) showed AVC progression over a median follow-up of 5.9 years (IQR 5.5-6.8). Sixteen major adverse cardiovascular events (MACE) occurred during follow-up. Of 231 with baseline AVC = 0, 29 (12.5%) developed new AVC. Progressors were more likely to be older (57.1 vs. 54.2 years, p=0.002), have diabetes mellitus (27.9% vs. 12.6%, p=0.009) or hypertension (65.6% vs. 31.3%, p<0.001), and had higher median 10-year ASCVD risk (10.8% vs. 5.3%, p<0.001). Median Lp(a) was higher among progressors [17.3 mg/dL (IQR 7.2–46.2)] vs. non-progressors [14.4 mg/dL (IQR 5.7–27.6)], and elevated Lp(a) >50 mg/dL was more common (21.3% vs. 8.9%, p=0.012).
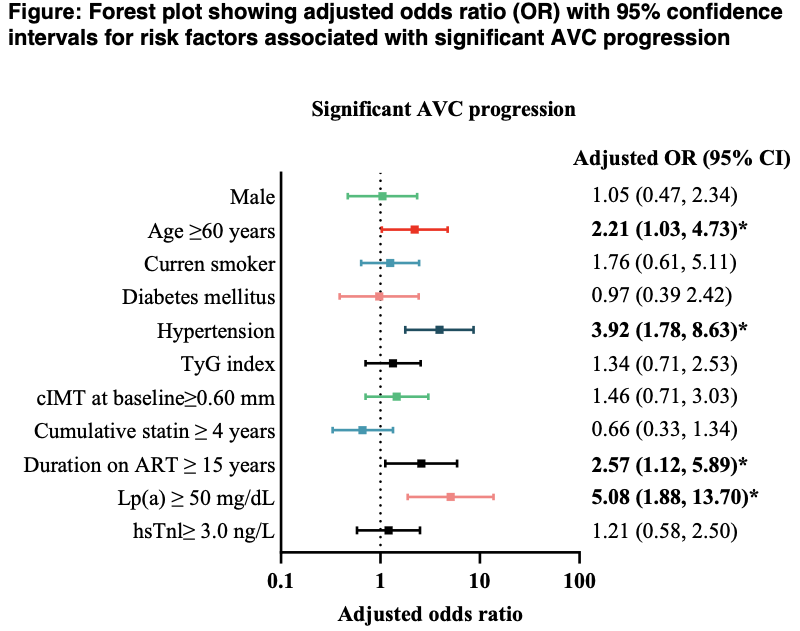
In multivariable analysis, independent predictors of AVC progression were: Lp(a) >50 mg/dL (aOR 5.08; 95% CI 1.88–13.7, p=0.001, Hypertension (aOR 3.92; 95% CI 1.78–8.63, p=0.001), , ART duration >15 years (aOR 2.57; 95% CI 1.12–5.89, p=0.025), and Age ≥60 years (aOR 2.21; 95% CI 1.03–4.73, p=0.04). Predictors of new AVC were Lp(a) >50 mg/dL (aOR 4.43), age ≥60 years (aOR 2.91), and hypertension (aOR 2.82).
Conclusions
In aging PLWH on long-term suppressive ART, elevated Lp(a) was an independent predictor of AVC progression alongside traditional risk factors. Future studies should evaluate whether Lp(a)-lowering therapies can mitigate AVC and atherosclerotic disease in PLWH.
Table or Figure