Background
Data on cabotegravir and rilpivirine (CAB/RPV) use are increasing, but little is known about outcomes after treatment discontinuation (TD). Aims of the study were to characterize switch regimens, to estimate the probability of TD after CAB/RPV discontinuation and to assess changes in immunologic and metabolic parameters during CAB/RPV vs. subsequent oral antiretroviral therapy (ART).
Methods
People with HIV (PWH) receiving CAB/RPV were enrolled in the prospective SCohoLART study (NCT05663580). Participants who had been followed up for more than one year after discontinuing CAB/RPV and therefore enrolled before July 2024 were included. TD was defined as switch to another regimen for any reason. TD probabilities were determined using Kaplan-Meier curves. Linear mixed models estimated monthly mean changes (slopes) with 95% confidence intervals (CI). Characteristics were reported as median (interquartile range) or frequency (%).
Results
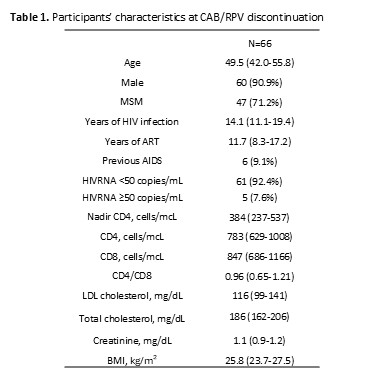
Overall, 66/509 PWH (13.0%) discontinued CAB/RPV after a median of 6 (2.5-10.3) months, mainly due to injection site reactions (27, 40.9%); 5 (7.6%) interrupted due to virological failure (VF). Of these 66 (Table 1), 100% switched to a single-tablet regimen (STR), including 40 (60.6%) to a 3-drug regimen and 26 (39.4%) to a 2-drug regimen; 53 (80.3%) received an integrase inhibitor-based ART. Overall, 55/66 (83.3%) resumed the oral ART prior to CAB/RPV, of which 33/66 (50%) with a three-drug ART. Over a median follow-up of 19.8 (14.6-26.0) months, 12 PWH (18.2%) experienced TD; the main cause was a reduction in the drug burden (4, 33.3%). No PWH switched due to VF. After CAB/RPV discontinuation, TD probabilities were 9.1% (95%CI, 4.2%-19.1%) at month 6, 15.2% at month 12 (8.5%-26.3%), and 18.9% at month 18 (11.2%-31.1%). Median monthly CD4 changes were slightly higher during CAB/RPV compared to oral ART [5.3 (–7.6; 18.1) vs. 2.1 (–4.8; 8.9) cells/µL], though not significant (p=0.649); similar trends were observed for CD8 [6.0 (–10.2; 22.3) vs. 4.8 (–2.6; 12.1) cells/µL, p=0.887]. Slopes per month in lipid parameters [LDL 0.04 (–1.83; 1.92) vs. –0.23 (–1.15; 0.69) mg/dL, p=0.802; total cholesterol 1.15 (–0.86; 3.17) vs. –0.09 (–1.29; 1.1) mg/dL, p=0.273] were minimal.
Conclusions
All participants who discontinued CAB/RPV switched to an STR, mainly composed of 3 drugs. The probability of TD in the months following CAB/RPV discontinuation was not negligible. Immunologic and metabolic trajectories showed no differences between CAB/RPV and subsequent oral ART.
Table or Figure