Background
The impact of antiretroviral therapy (ART) on renal preservation is critical for persons with HIV (PWH) post-renal transplant. Clinical trials have demonstrated B/F/TAF is safe and efficacious, with low risk of renal toxicity. Little is known about its pharmacokinetics (PK) in PWH post-renal transplant.
Methods
Single arm, open-label, switch study among virally suppressed (HIV VL < 50 c/mL) PWH post renal transplant, switched from baseline ART to B/F/TAF and followed for 72 weeks. Baseline and monitoring of renal function (CrCl), viral efficacy (HIV VL), and tacrolimus (TAC) trough concentrations were collected. At week 12, intensive PK samples were collected at hrs 0, 0.5, 1, 2, 4 and 24, and analyzed for plasma BIC, FTC, TAF, and TFV; samples at 0, 4, and 24 hrs were analyzed for TFV-DP and FTC-TP in PBMC and DBS. Plasma AUC, Cmax, and Ctrough were determined with non-compartmental methods; Css was calculated for TFV-DP and FTC-TP. Plasma PK values were compared with PWH with similar renal function [package inserts]; TFV-DP and FTC-TP were compared with PWH values from QUANTI-TAF [NCT04065347; controls].
Results
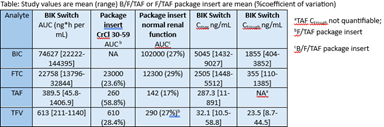
Final results included 19 subjects, 18 with evaluable PK, mean age 56 [range 38 – 69] yrs; 13 male; 17 Black; 8 transplanted in Hope in Action initiative. There were no statistical differences observed in the means of renal safety parameters. Mean CrCl day 1 vs week 72: 54.9 vs 60.9 mL/min, p=0.11. Tacrolimus (TAC) trough concentrations remained stable, without need for dose adjustment. HIV viral suppression was maintained in all (< 50 c/mL). Plasma PK AUC were comparable to historical data in PWH with similar renal function (CrCl 30-59ml/min; Table), which were approximately 2-fold higher than values in PWH with normal renal function, as expected. The CrCl was higher in QUANTI-TAF controls (mean >60ml/min) than study. Geometric mean for TFV-DP in DBS was 5775 (study) and 3386 (controls) fmol/punches, and PBMC was 1637 (study) 570 (controls) fmol/106 cells and that for FTC-TP in PBMC was 15.4 (study) and 5.6 (controls) pmol/106 cells.
Conclusions
BIC, TAF, TFV, and FTC AUCs were comparable to historical data for PWH with CrCl between 30-60ml/min for which B/F/TAF is indicated. The higher concentrations for TFV-DP and FTC-TP were commensurate with plasma increases for CrCl of 30-60ml/min. CrCl and TAC doses remained stable throughout and HIV remained suppressed at 72 weeks. B/F/TAF demonstrated a high safety margin and was efficacious in PWH status post-renal transplant.
Table or Figure