Background:
Histoplasmosis burden in advanced HIV disease (AHD) in Southeast Asia is unknown due to the lack of diagnostics. We report results of an ongoing multi-center prospective histoplasmosis diagnostic validation study in patients with AHD in Vietnam.
Methods:
We recruited hospitalized HIV-infected adults, CD4 count ≤ 100 cells/µL or WHO stage 3 or 4 disease, ART-naive or on ART for ≤ 3 months or >12 months from 3 hospitals in Vietnam. All patients were screened for Histoplasma antigen using the IMMY Clarus Histoplasma GM enzyme immunoassay (HAg EIA) in urine and Myco/F Lytic blood culture (over 6 weeks), alongside conventional microscopy and cultures of other specimens as clinically indicated. Proven histoplasmosis was defined as culture-positive disease. Probable histoplasmosis was defined as a compatible clinical syndrome and resolution of HAg levels on antifungal therapy. Patients were followed up monthly for over 6 months.
Results:
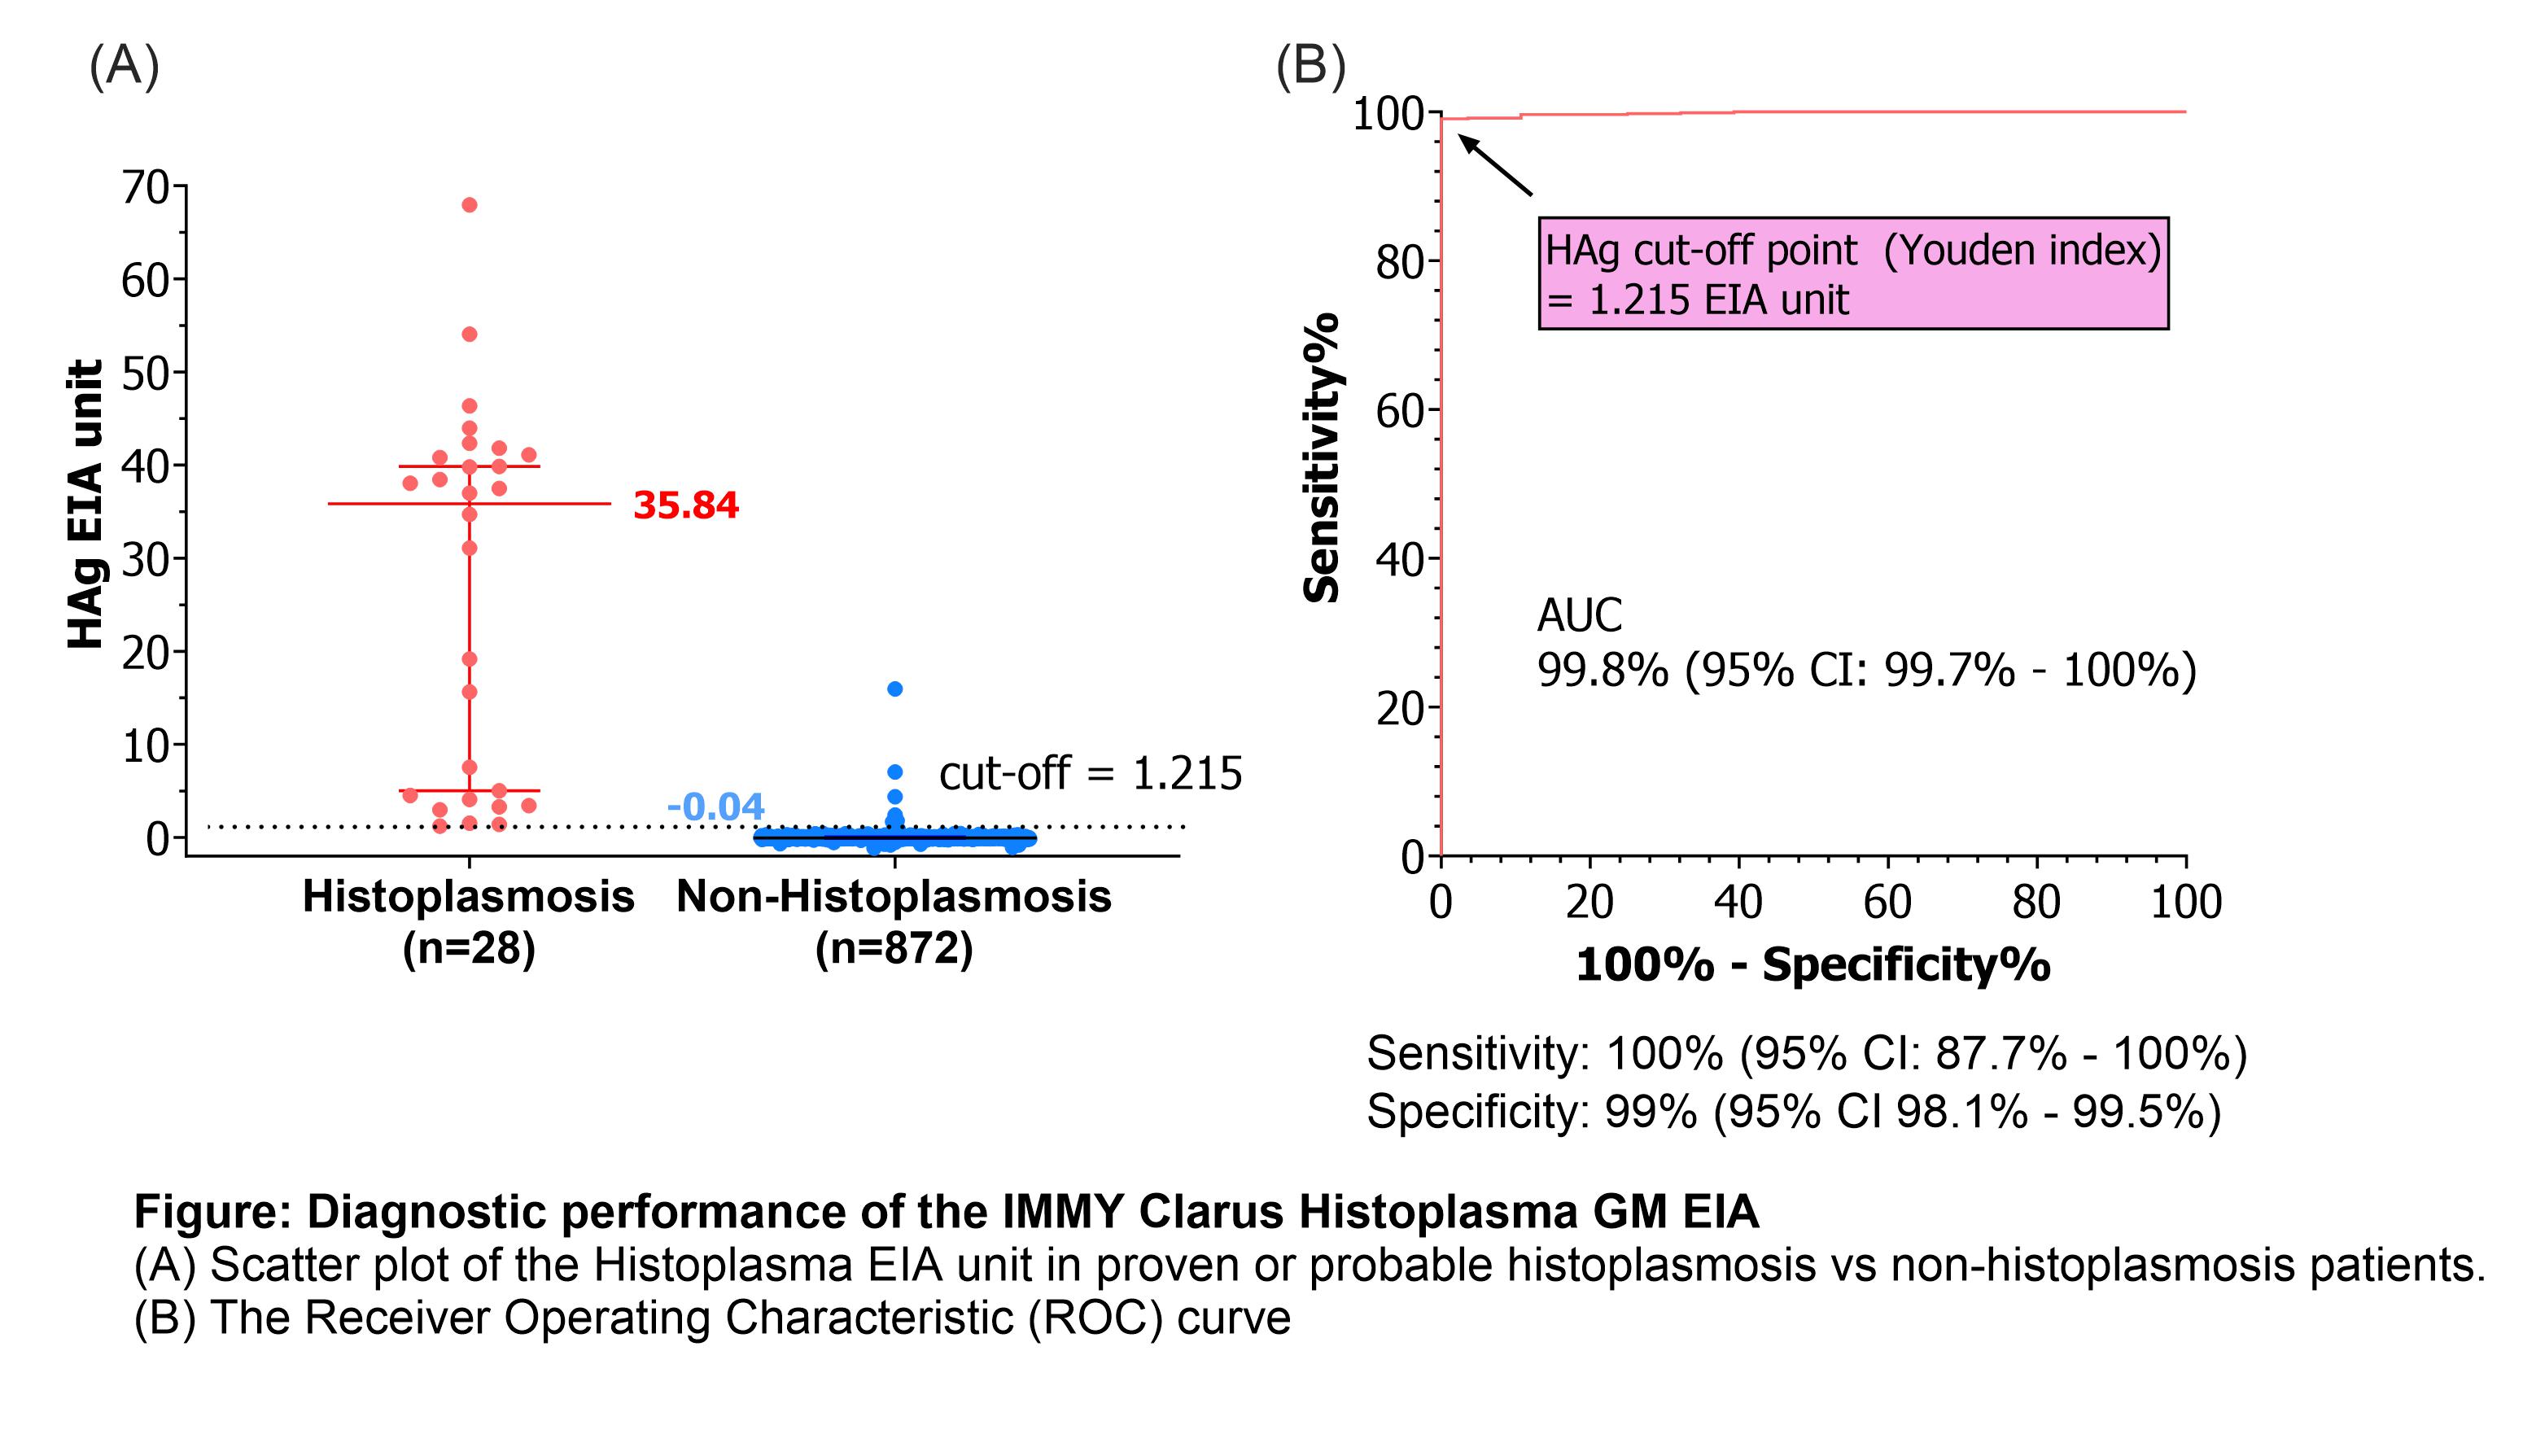
900 patients were recruited between 02/2021 and 08/2023. Overall prevalence of HAg positivity was 37/900 (4.1%) and was higher in southern vs. northern Vietnam, 30/581(5.2%) vs. 7/319 (2.2%), P= 0.035, Fisher Exact. Among the 37 HAg-positive patients, 15 (40.5%) had proven histoplasmosis; 13 (35.1%) had probable histoplasmosis; and 9 (24.3%) did not develop disease over 6 months. The median HAg EIA unit of proven and probable histoplasmosis patients was 35.84 (IQR 4.31 to 40.96) compared to -0.04 (IQR -0.08 to 0.03) of non-histoplasmosis patients, P<0.001, Mann-Whitney. At a cut-off EIA unit of 1.2, HAg EIA had 100% sensitivity (95% CI: 87.7% - 100%), 99% specificity (95% CI 98.1% - 99.5%), 75.7% positive predictive value (95% CI 61.9% - 85.6%), 100% negative predictive value (95% CI 99.6% - 100%), and an accuracy of 99.8% (95% CI: 99.7% – 100%). Among 28 histoplasmosis patients, the median CD4 count was 17 (IQR, 7 - 31) cells/μL. H. capsulatum was isolated from blood in 12 (42.9%), bone marrow in 11 (39.3%), skin lesions in 1 (3.6%) patients. Median time to culture positivity in bone marrow and blood was: 10.5 (IQR, 7 – 16.5) days and 17 (IQR, 11.5 – 19) days, P=0.160, Wilcoxon. 7/28 (25%) patients died by month 6 despite antifungal therapy.
Conclusions:
Our study demonstrates an excellent diagnostic performance of the HAg EIA and unveils a substantial burden of histoplasmosis in AHD in Vietnam. The mortality remains high (25%) despite antifungal therapy, highlighting the need to screen for Histoplasma antigen, preferably before patients become symptomatic.