Background:
No oral solid fixed-dose combination (FDC) antiretroviral dispersible formulations are available for HIV prevention or treatment from birth. Neonates could benefit from existing pediatric antiretroviral solid formulations. We evaluated the pharmacokinetics (PK) and safety of pediatric ABC/3TC dispersible tablets and LPV/r (2-in-1) granules in term neonates exposed to HIV, birth weights ≥2.0 to £4.0 kg.
Methods:
The ‘PETITE’ study was a phase I/II, open-label, single arm, clinical trial in South Africa evaluating oral ABC/3TC (120/60 mg) dispersible tablets and LPV/r (40/10mg) granules. Neonates stratified by birth weight received 30/15 mg of ABC/3TC daily (¼ dispersible tablet) and 80/20 mg of LPV/r twice daily (2 sachets) from birth through 28 days. Two intensive PK sampling visits were performed: one at < 14 days of life and after ≥ 72 hours of treatment (PK1), and another 10-14 days later (PK2). Safety visits were performed 1-2 week(s) after each PK visit. Electrocardiograms (ECGs) were performed at baseline and during follow-up.
Results:
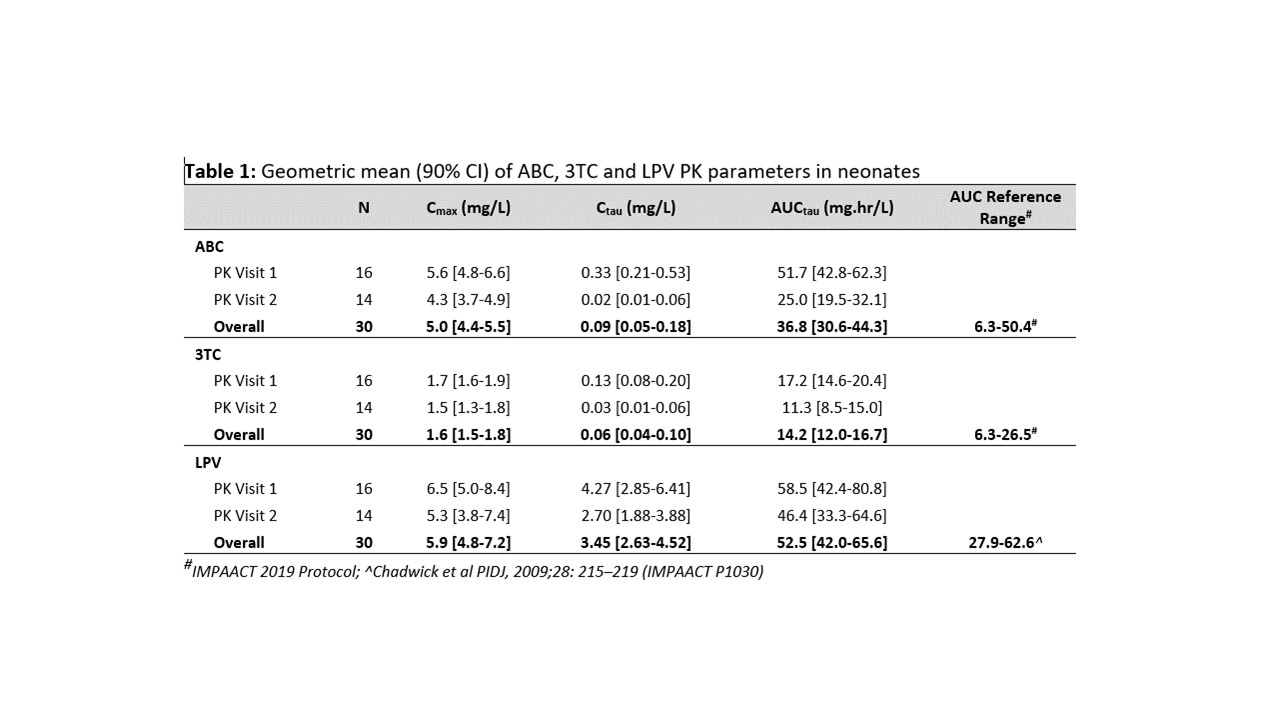
Sixteen neonates (15 breastfed) started ABC/3TC + LPV/r within 3 days of life, median (range) birth weight was 3.1 (2.2-3.8) kg. PK1 and PK2 visits were performed between 6-14 and 19-24 days of life, respectively; 2 neonates did not complete PK2. ABC, 3TC doses were 9 (7-13), 4 (3-7) mg/kg once daily, LPV dose was 377 (307-480) mg/m2 twice daily. Geometric mean (GM, 90% CI) AUC0-24 of ABC, 3TC and LPV were higher at PK1 versus PK2 – Table 1. ABC exposures at PK1 crossed the upper target reference range but rapidly decreased to within range by 2-3 weeks of life. 3TC and LPV exposures were within the reported ranges for young infants. Geometric mean ABC, 3TC, and LPV AUC0-24 were also higher in neonates with birth weights 2-3 kg compared to 3-4 kg, 43.1 vs 31.5, 17.9 vs 11.2 and 63.4 vs 43.4 mg.hr/L, respectively. No Grade 2 or higher adverse events were related to study drug. All ECGs were normal except for a single Grade 1 prolonged QTcF interval which spontaneously resolved.
Conclusions:
Initiating pediatric solid FDCs of once daily ABC/3TC dispersible tablets in combination with twice daily LPV/r granules from birth was safe and well tolerated. ABC and 3TC drug exposures were initially high but rapidly decreased. LPV exposures were lower than in adults but comparable to young infants receiving LPV/r liquid. This study supports giving solid dispersible FDCs from birth for HIV prevention and treatment in neonates.