Background
The IMPAACT 2010 (VESTED) randomized trial compared dolutegravir (DTG) plus emtricitabine/tenofovir alafenamide fumarate (FTC/TAF); DTG plus FTC/tenofovir disoproxil fumarate (TDF) and efavirenz (EFV)/FTC/TDF initiated during pregnancy among 643 women in 9 countries (predominantly in Africa). Previous analyses showed superior virologic efficacy and pregnancy outcomes with DTG-based compared with EFV-based ART. We conducted an exploratory analysis of infant mortality through 50 weeks after birth, and associated maternal and infant factors.
Methods
We estimated the probability of death through 50 weeks after birth among liveborn infants, overall and by randomized maternal ART regimen, using the Kaplan–Meier method. We examined potential maternal risk factors (baseline gestational age, CD4 count, and viral load at enrollment; and antepartum weight gain, folate, and HbA1c) and infant risk factors (preterm birth, low birth weight [LBW], small-for-gestational-age [SGA], major congenital anomaly, HIV infection) for infant mortality in univariable log-binomial models.
Results
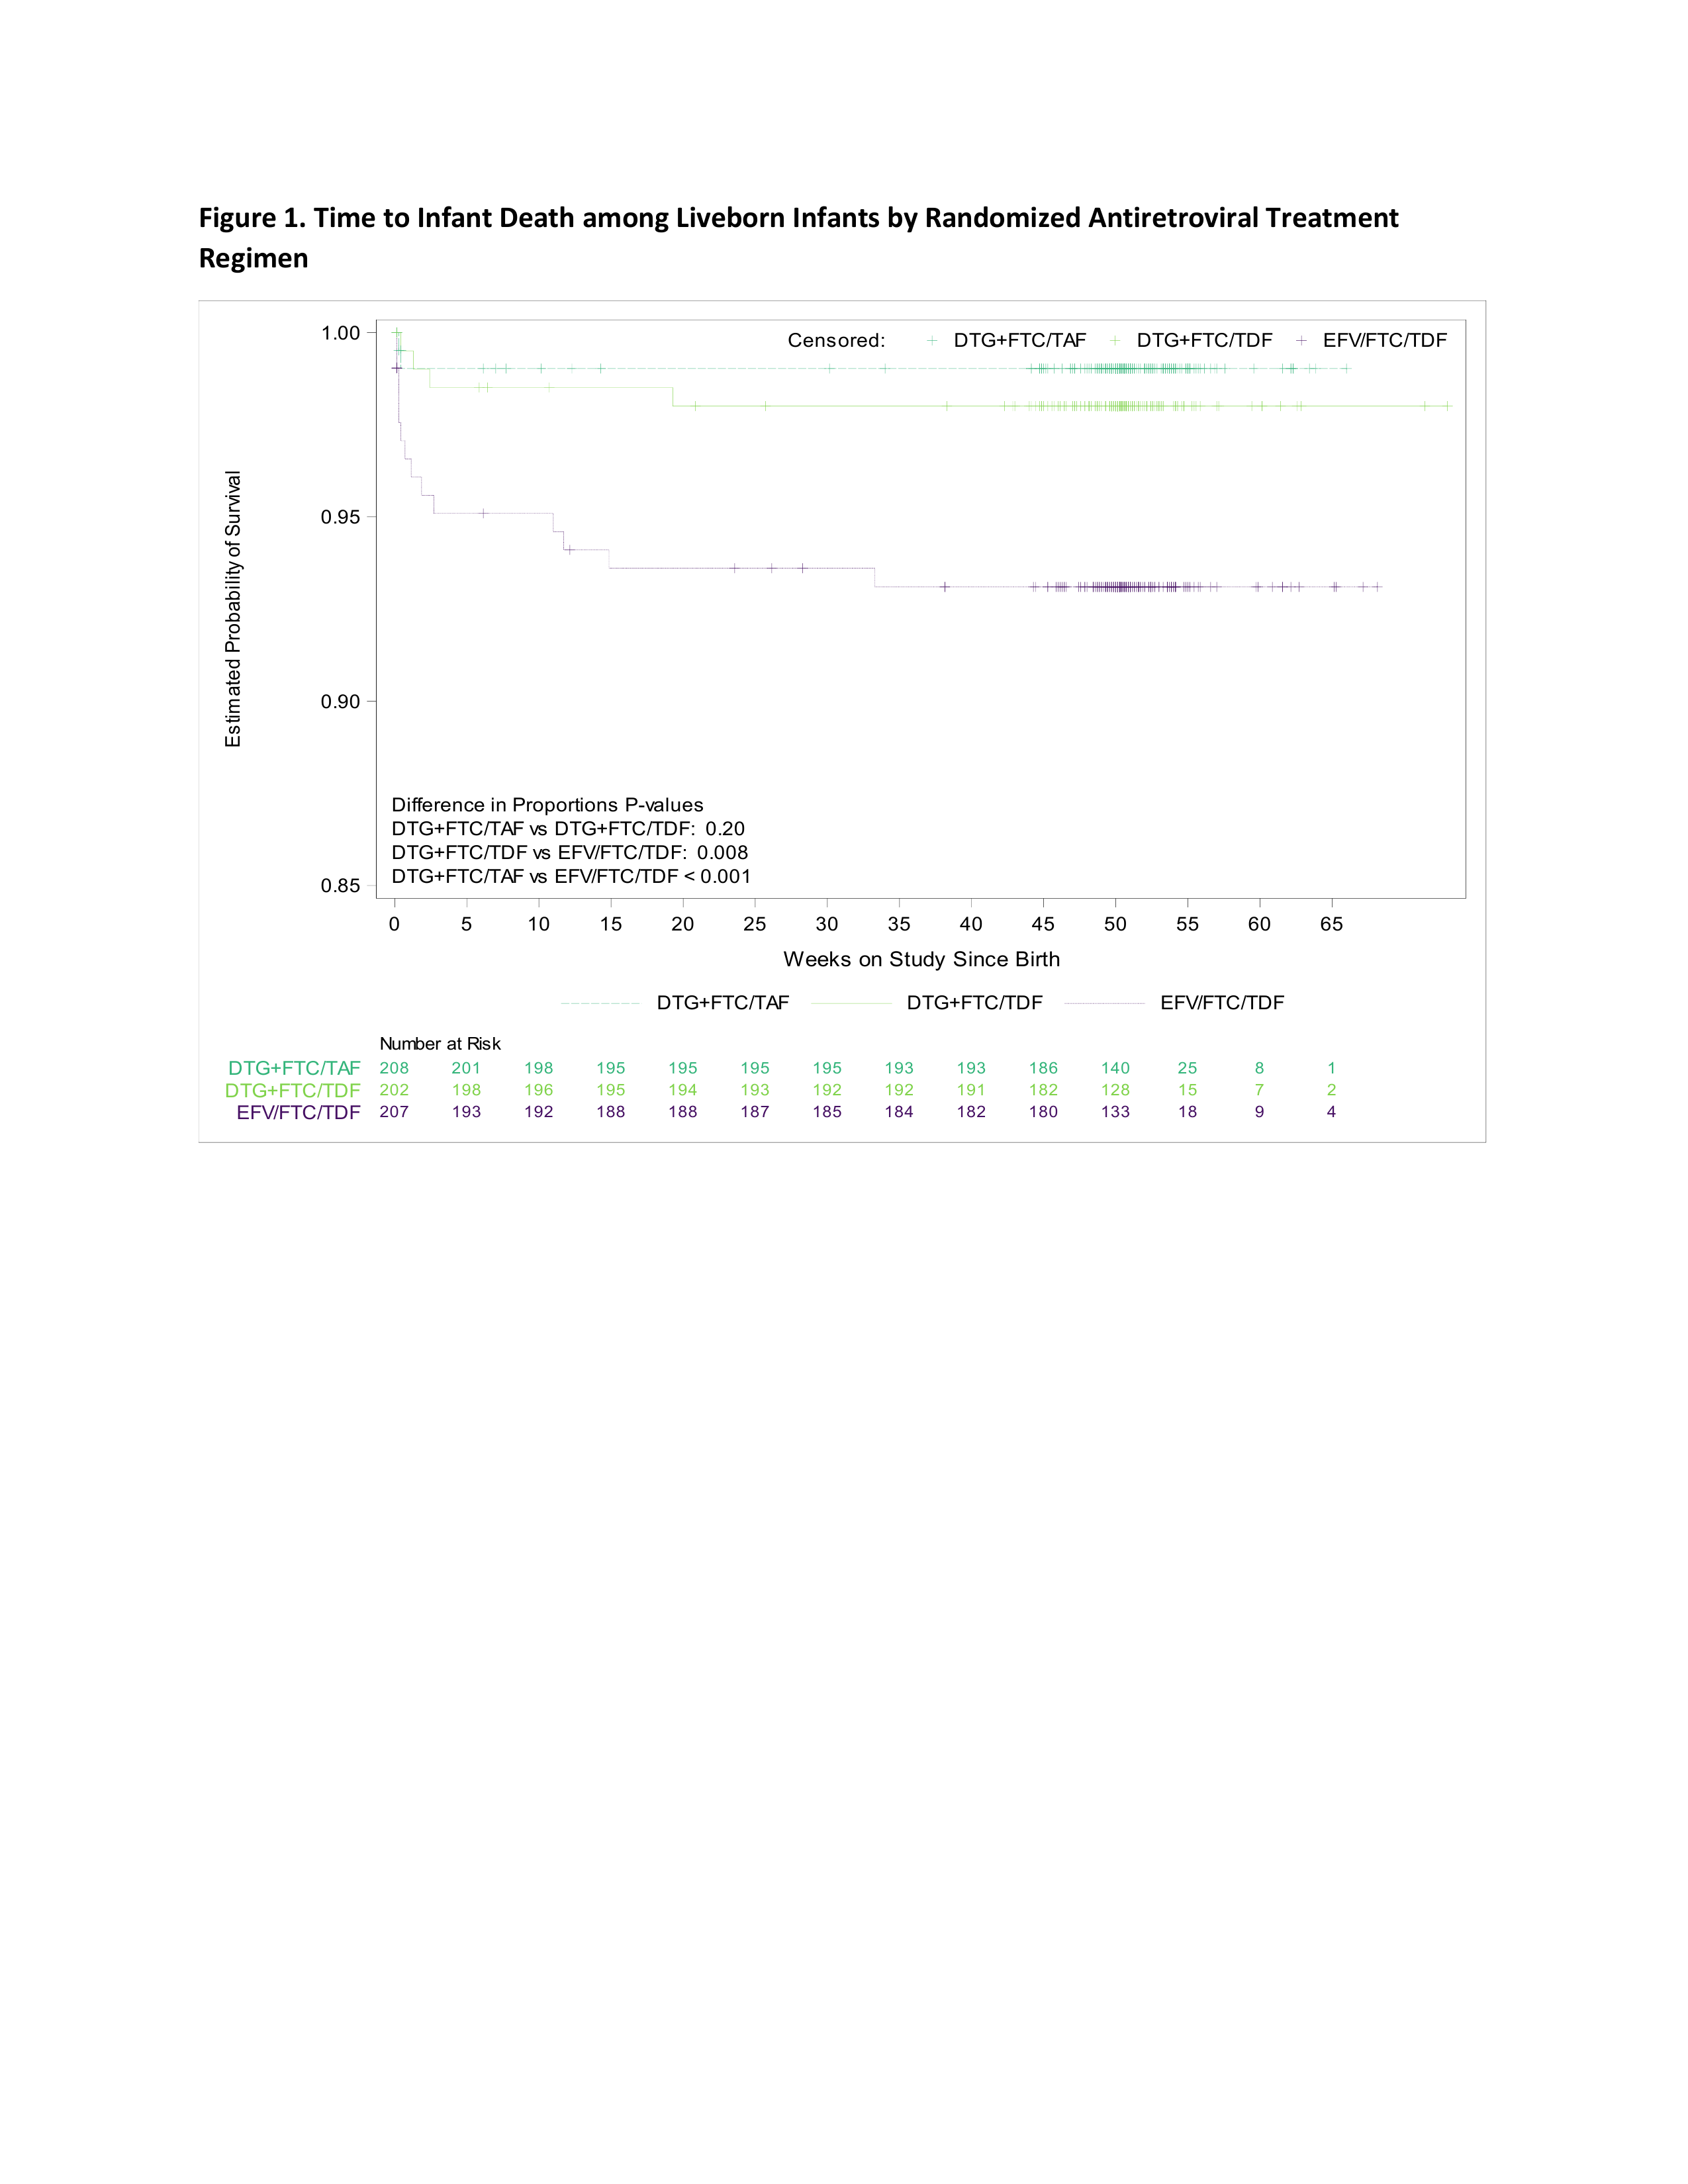
Of 640 deliveries, 23 (3.6%) were stillborn and were excluded from this analysis (4 EFV/FTC/TDF, 8 DTG+FTC/TAF, 11 DTG/FTC/TDF). Twenty of 617 liveborn infants (3.3%) died by 50 weeks, with 15 (75%) deaths occurring within the first 28 days. Mortality was higher among EFV/FTC/TDF-exposed infants (6.9%) compared with DTG+FTC/TAF (1.0%; difference 5.9%, 95%CI 2.2%,9.7%) and DTG+FTC/TDF (2.0%; difference 4.9%, 95%CI 0.9%,8.9%) [Figure 1]. We estimated higher mortality for infants of mothers with lower baseline CD4 count (<500 vs. ≥500 cells/mm3; RR 2.34, 95%CI 0.86,6.35) and higher maternal viral load at delivery (>1,000 vs. <50 copies/mL; RR 4.5, 95%CI 1.2,17.5). Infant risk factors strongly associated with mortality included preterm birth (RR 6.6, 95%CI: 2.8,15.4), LBW (RR 6.8, 95%CI: 2.7,17.2), SGA (RR 2.8, 95% CI: 1.1,7.3), congenital anomalies (RR 8.1, 95%CI: 1.4, 46.6), and infant HIV infection (RR 8.1, 95%CI: 1.4,46.6).
Conclusions
Over 3% of liveborn infants died by 50 weeks. Predictors of mortality included lower maternal CD4, higher viral load, and EFV/F/TDF in pregnancy, in addition to the known risk factors of preterm birth, LBW, and SGA. Findings highlight the importance of optimized maternal ART regimens, viral suppression, and preserved CD4 cell count in pregnancy, and targeted neonatal care to reduce infant mortality.
Table or Figure