Background
Approximately one-third of Tanzanians living with HIV are aged ≥50. Aging persons living with HIV (PLWH) are at a higher risk of multi-morbidities compared to older persons without HIV. Multi-morbidities can have a significant negative impact on quality of life (QOL). This study assessed the distribution of geriatric and medical comorbidities and their association with quality of life in older PLWH in Tanzania. These results are important to understand the growing complexities of care needs in this population and inform future strategies to improve health and well-being.
Methods
This cross-sectional study was conducted among PLWH at seven HIV clinics in Dar es Salaam, Tanzania. Participants were included if they were aged ≥50 years, on ART ≥3 years, and in HIV care ≥12 months. Geriatric comorbidity screening included Fried’s Frailty phenotype score (frailty), PHQ-9 (depression), community screening interview for dementia (CSI-D), and WHODAS 2.0 (ADLs). QOL was assessed using the WHOQOL-HIV-BREF. Fasting blood glucose, lipid profile, and serum creatinine were also measured. Multivariable linear regression was used to examine the association between geriatric and medical comorbidities and QOL scores.
Results
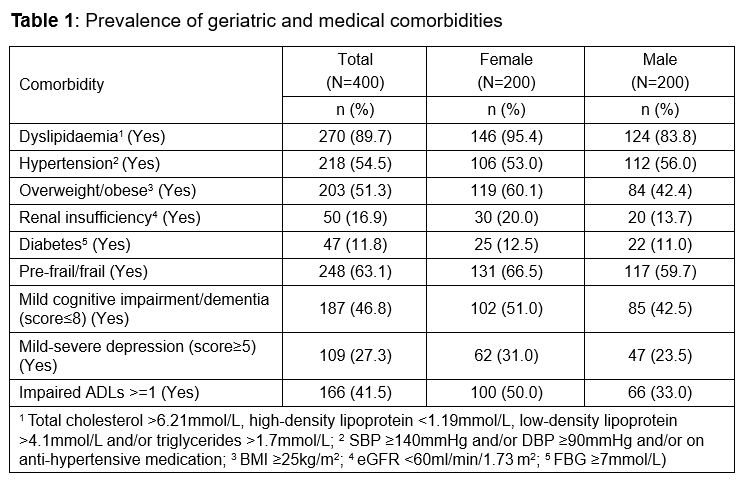
A total of 400 older PLWH were enrolled [mean age (SD): 58.6 (±6.9) years; 50% female; mean (SD) duration on ART: 11.8 (±1.8) years]. Among these, 86% were on Dolutegravir (DTG)-based ART, and 73% were virally suppressed (<50 copies/mL). The prevalences of geriatric and medical comorbidities are given in Table 1. Dyslipidemia, hypertension, and pre-frailty/frailty were observed in over 50% of PLWH. The mean (SD) QOL score was 74.2 (±12.2), with the highest scores in physical, spiritual, and social relationships domains. Pre-frailty (β=-4.70, 95% CI:-7.31,-2.07, p<0.01) and frailty (β=-5.52, 95% CI: -9.81,-1.23, p=0.01); ≥1 impaired ADLs (β=-6.34, 95% CI:-9.04,-3.64, p<0.01); mild depression (β=-9.06, 95% CI:-11.90,-6.21, p<0.01) and moderate/severe depression (β=-16.67, 95% CI:-21.39,-11.94, p<0.01) were associated with worse QOL.
Conclusions
A high prevalence of geriatric and medical comorbidities in aging PLWH in Tanzania was observed, several of which were associated with lower QOL. These findings highlight the need to implement the screening and prevention of geriatric clinical and psychosocial conditions in PLWH aged ≥50 into routine care.
Table or Figure