Background
9-valent HPV vaccine is effective as a prevention tool, rather than therapeutic at cervical site. Insights on viral clearance at anal site is still unknown, especially in the high-risk population of MSM with HIV. Aim of the study is to determine factors associated with the clearance of at least one genotype included in the 9-valent vaccine.
Methods
Retrospective cohort analysis in MSM with HIV in care for HIV at the Infectious Diseases Unit of San Raffaele Hospital, Milan, Italy, with ≥2 HPV tests on anal swabs collected 1 before and 1 after immunization with 9-valent HPV vaccine, from 2014 and December 2023 (data lock). Characteristics were determined within 180 days from the date of HPV testing. HPV genotypes are detected by multiplex real-time PCR (CFX96™, Seegene). Multivariable logistic regression is used to estimate risk factors associated with clearance of ≥1 HPV genotype included in the 9-valent vaccine.
Results
Among 393 MSM with HIV with at least one HPV test pre-immunization, 96 (24.4%) have a subsequent one post-vaccine. At their last HPV test, those who cleared at least one HPV genotype included in 9-valent vaccine were 48 (50%), with a median (IQR) age of 35.1 (31.1-42.5) years, as compared to those who did not [39.9 (34.9-44.1)].
Immuno-virological characteristics were similar among the two groups: overall median CD4 nadir was 410 (285-558) cells/uL with 14.7% with CD4 ≤200 cells/uL, CD4+ count 787 (614-938.5) cells/uL, CD4/CD8 ratio 1.00 (0.8-1.2), on ART since 7.6 (5.4-10.2) years. Sexually transmitted infections (STI), including syphilis, gonorrhea, mpox, chlamydia, were frequent in both groups: overall, 52 (54.7%) and 19 (20%) had a history or a concomitant STI, respectively.
Median time between the two HPV test considered was 1470 (1125-1736) days. Among those with prior positive results, HPV-16 and -18 were cleared in 9/25 and 4/12 MSM with HIV. On the other hand, 11 and 6 had a positivization for HPV-16 and -18.
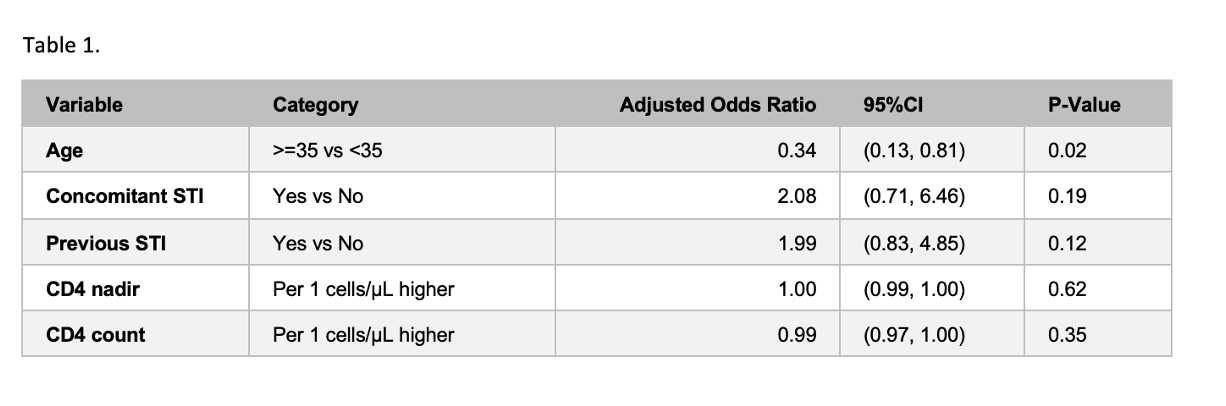
At multivariate regression (table 1), the risk of clearance of ≥1 HPV genotype included in the 9-valent vaccine was lower in younger (<35 years) people.
Conclusions
These results emphasize the importance of age in virus clearance among immunized individuals. We endorse consensus guidelines recommending anal cancer screening start at age 35 for MSM with HIV, as viral persistence is more likely in this group.
Table or Figure