Background
Cardiovascular disease (CVD) risk is higher in people with HIV (PWH) than people without HIV. However, whether this elevated risk of CVD is present in antiretroviral therapy (ART)-naïve PWH with high CD4+ counts, and whether delayed initiation of ART worsens CVD outcomes is unknown.
Methods
The Strategic Timing of Antiretroviral Treatment (START) study randomized ART-naïve adults with HIV and CD4+ counts>500 cells/µL to immediate vs. deferred (until CD4 count <350/µL or AIDS developed) ART initiation. We report CVD event rates (composite of MI, stroke, coronary revascularization, or death from CVD) between treatment arms in three time periods: (i) pre-2016 (ART use differed by treatment arm); (ii) post-2016 (study was unblinded and continuous ART use was recommended for both groups, 2016-2021); and (iii) over the entire study. Subgroup analyses were performed according to baseline demographic, clinical characteristics and CVD risk factors. Time-to-event methods compared event rates between study arms.
Results
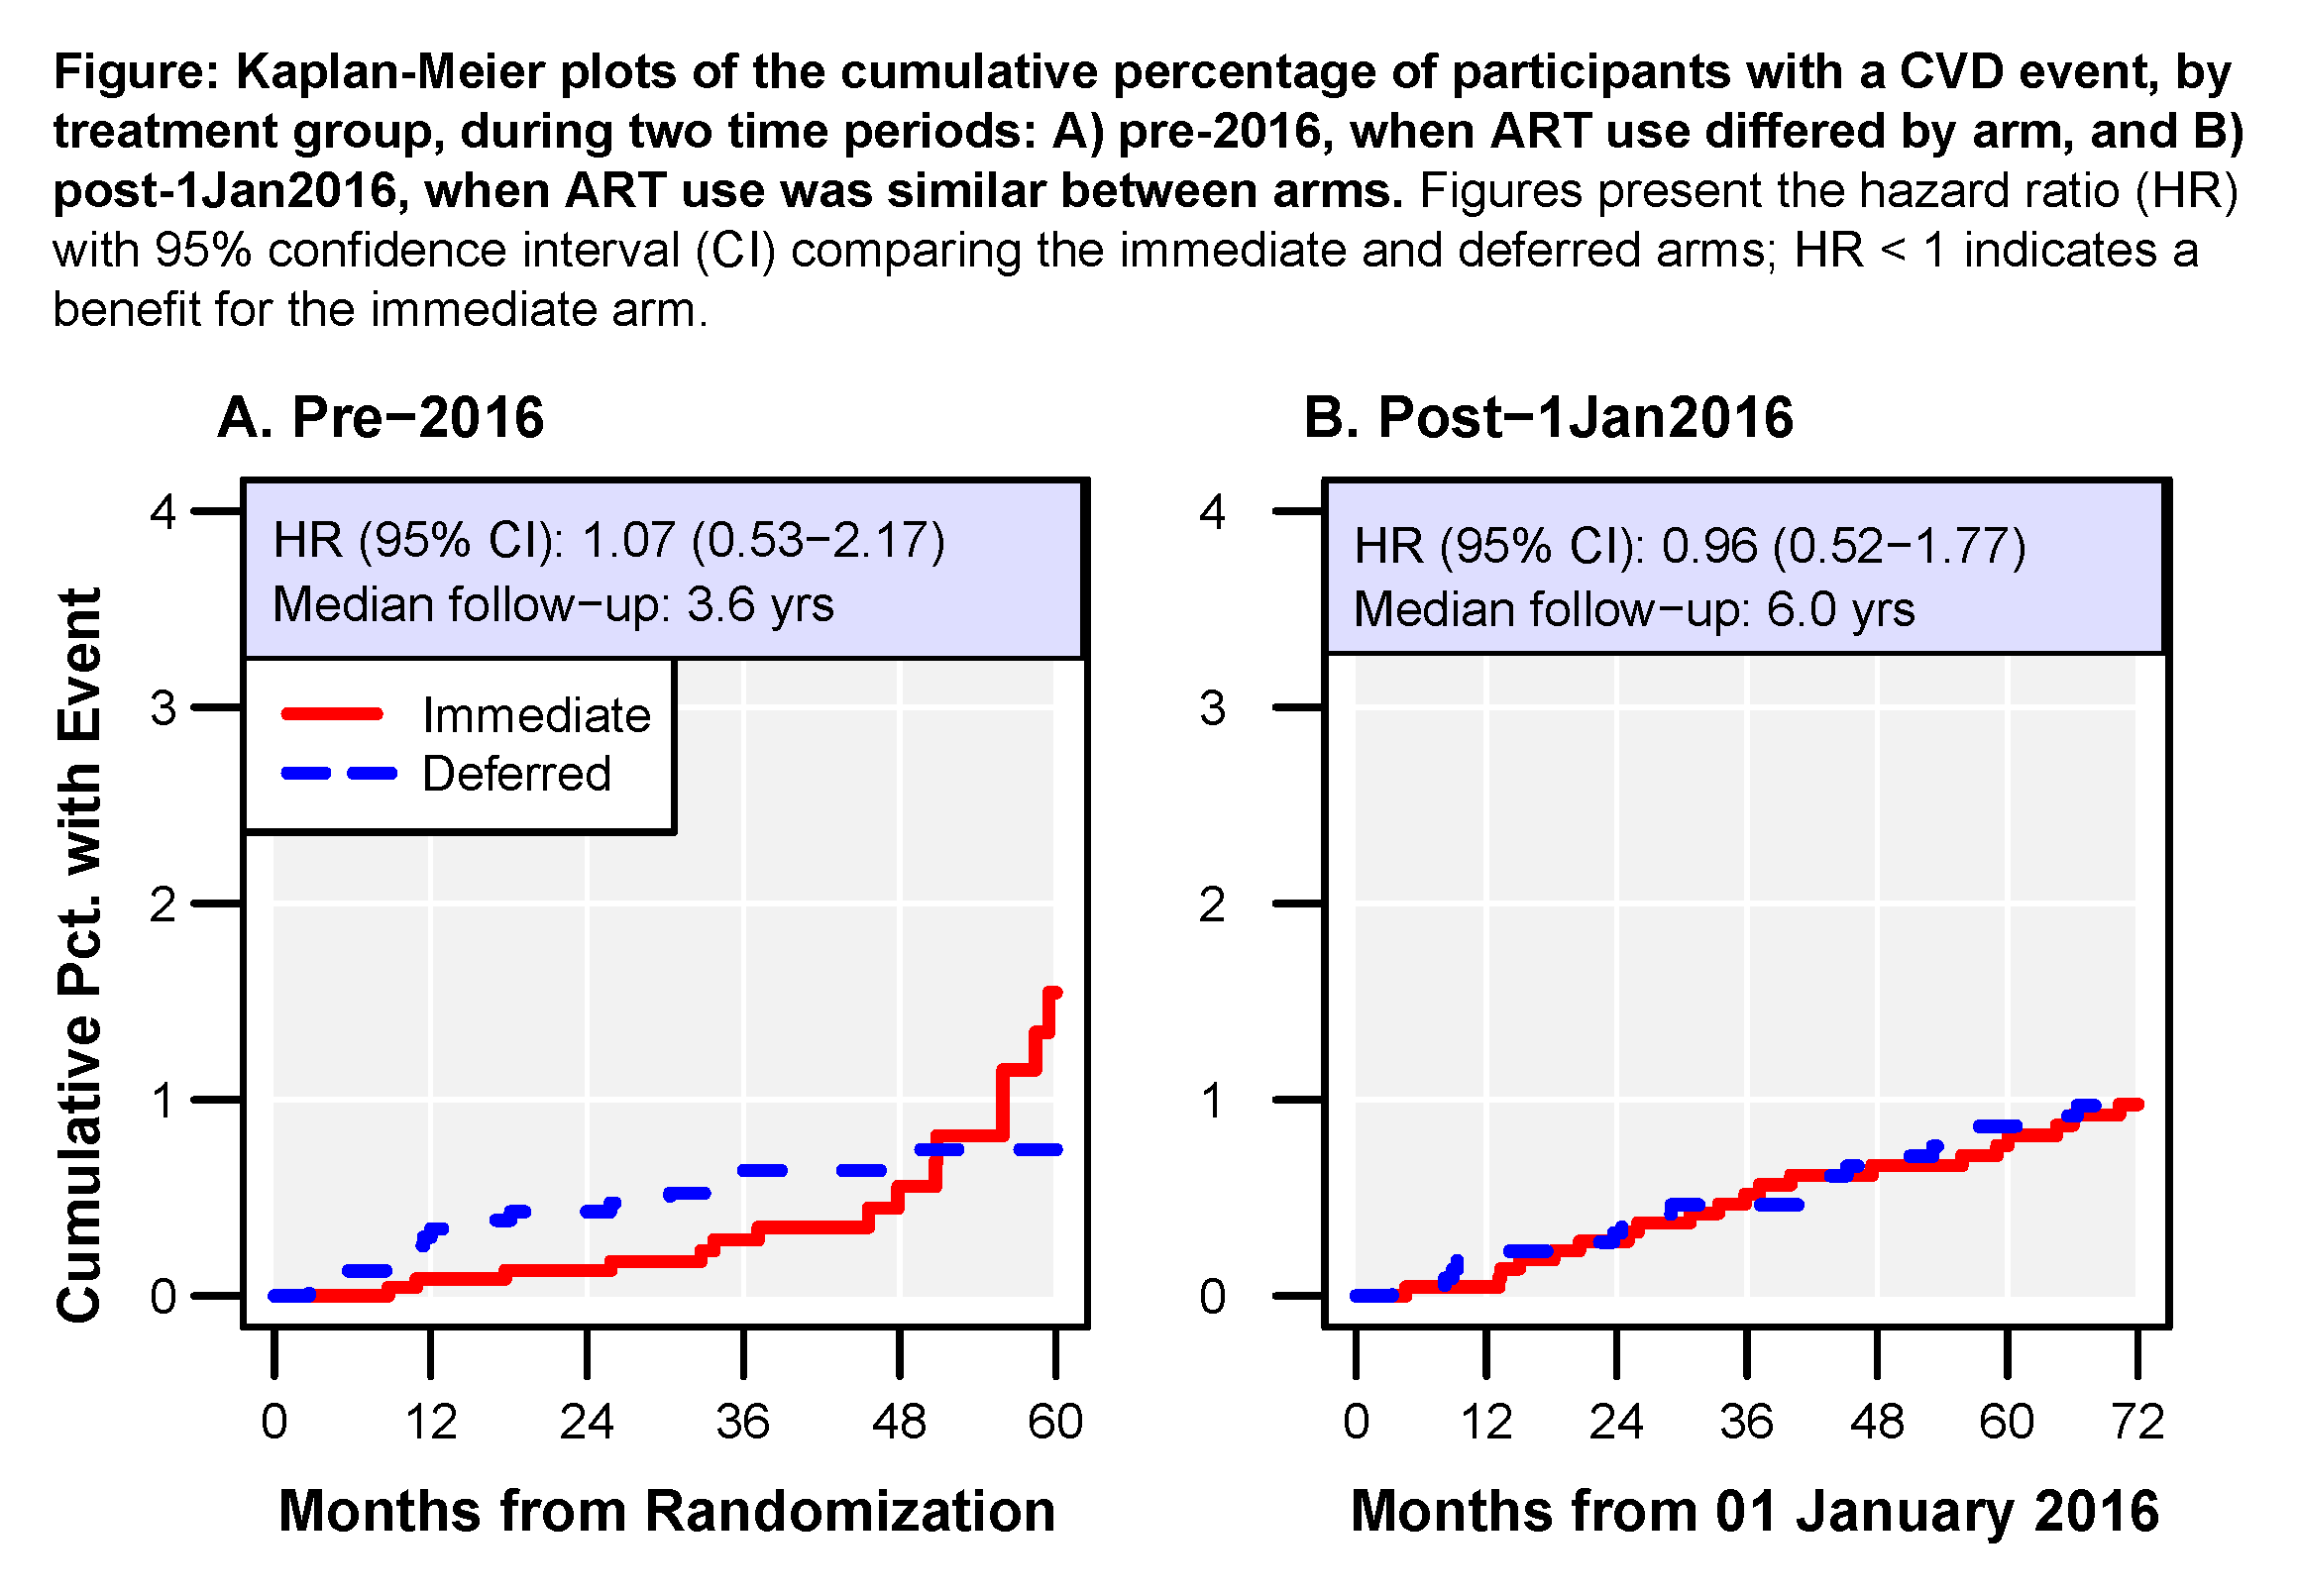
Overall, 4,684 participants were randomized (median age 36 yrs, 27% female, 30% Black race); 4436 (95%) had data available after 2016. At baseline, 32% were smokers, 17% had a BMI≥30 kg/m2, and the median Framingham 10-yr risk score was 1.9%. Comorbidities included hypertension (19%), dyslipidemia (8%), and diabetes (3%); 0.8% had prior CVD. Composite CVD event rates were similar between treatment arms during the pre- and post-2016 periods: 0.18 and 0.17 per 100 person yrs (PY) pre-2016 in the immediate and deferred arms, respectively, and 0.16 and 0.17 per 100 PY post-2016 in the immediate and deferred arms, respectively (Figure 1). Over the entire study (median follow-up of 9.3 yrs), 71 participants (35 immediate, 36 deferred) had a CVD event. There was no difference in events between arms (immediate/deferred hazard ratio [HR] 0.98; 95% confidence interval [CI] 0.61-1.56) for the composite CVD outcome or its components. Immediate vs. deferred ART was associated with a reduced risk of CVD in women (HR 0.19; CI 0.04-0.86) but not in men (HR 1.33; CI 0.79-2.24), p-value for interaction=0.014; interpretation is limited by low numbers of events.
Conclusions
While immediate ART is known to reduce the risk of many clinical comorbidities and adverse outcomes among PWH, we did not find an effect of early ART initiation for reduction of CVD events among individuals at low CVD risk and moderate to high CD4 counts in the START study. The benefit found among women warrants further evaluation.
Table or Figure