Background
Advanced HIV disease (AHD) is defined by WHO as CD4 count <200 cells/ µL or WHO stage 3-4, triggering a series of interventions to identify and treat opportunistic infections (OIs) and rapidly initiate ART. Access to CD4 count testing is declining as a ‘test and treat’ approach to HIV is adopted, and clinical features increasingly relied on to guide OI screening. We hypothesise that clinical features alone cannot accurately identify patients with CD4 count <200 cells/ µL, resulting in underdiagnosis of AHD.
Methods
We collected data from a prospective cohort study of adults attending a clinic in Soweto, Johannesburg following a positive HIV test. A logistic regression model was used to determine clinical features associated with low CD4 count (<200 cells/µL). A clinical scoring system was devised using model coefficients as weights and the Youden index to calculate optimal cut off.
Results
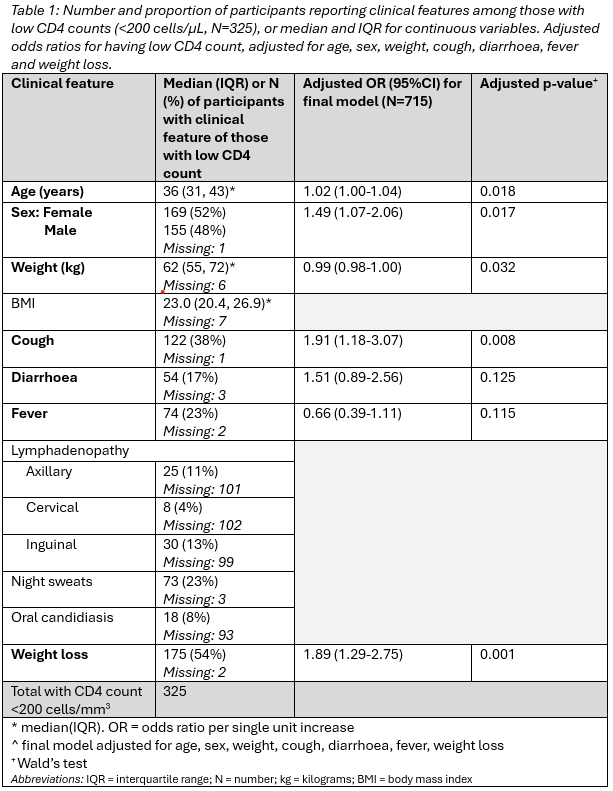
Data were available for 733 participants: age range 17-73 years, 60% female (442/733), median CD4 count 231 cells/µL, 44% (325/733) had CD4 counts <200 cells/µL. 12/14 assessed variables were crudely associated with CD4 <200/µL, though following adjustment, only cough, weight loss, male sex and age remained significant (Table 1). Weight loss and cough interacted; presence of cough without weight loss did not increase odds of CD4 <200 cells/µL (OR 0.91, 95%CI 0.45-1.89, p=0.80), whereas cough with weight loss increased odds significantly (OR 2.03, 95%CI 1.24-3.32, p=0.005). The final adjusted model included age, sex, weight, cough, diarrhoea, fever and weight loss, but was a poor fit: pseudo R2=0.08. Including self-reported WHO stage 3-4 OIs(7/733) to create a predictive model, the optimal score identified had specificity of 82% but poor sensitivity of 48%. Of those identified by this model, 156/230 (68%) had CD4 count <200 cells/µL; 169/325 (52%) with CD4 <200 cells/µL were not identified by the score. At one month follow up, all deaths occurred in those with CD4 counts <200 cells/µL (5/318, 1.6%; 7 lost to follow up).
Conclusions
Clinical features are associated with CD4 count <200 cells/µL in patients newly diagnosed with HIV, but cannot reliably identify AHD, even when combined with WHO staging. A clinical scoring system without CD4 count would result in underdiagnosis of AHD in around a half of patients with low CD4 counts, and inappropriate diagnosis in around a fifth of patients with CD4 counts of >200 cells/µL.
Table or Figure